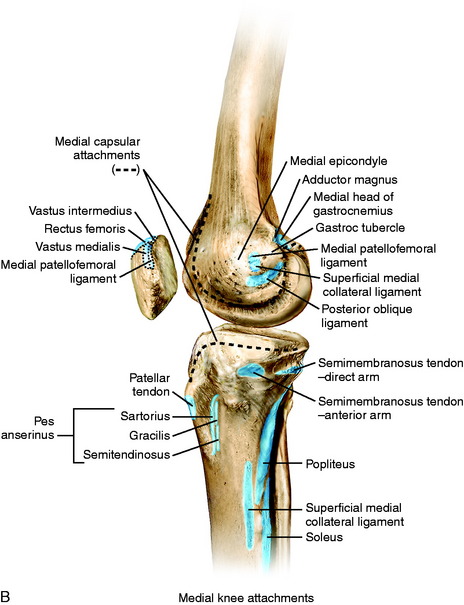
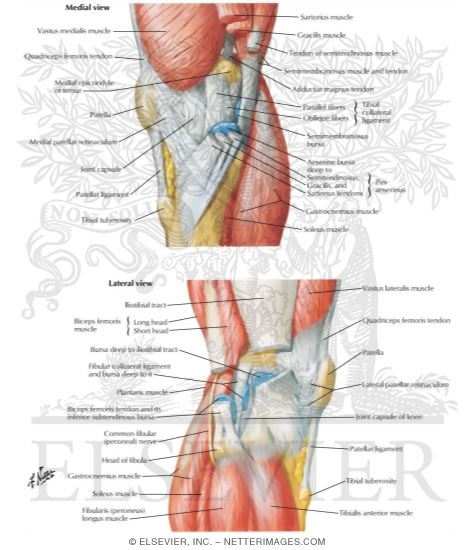
The medial gutter of the knee is a critical anatomical region that plays a pivotal role in joint stability, load transmission, and proprioception. Often overshadowed by more commonly discussed structures like the anterior cruciate ligament (ACL) or menisci, the medial gutter—also referred to as the medial compartment recess or medial synovial fold—is a complex space within the knee joint that houses vital soft tissue structures essential for smooth articulation and biomechanical function. Understanding its anatomy is fundamental for clinicians, physical therapists, and athletes alike, particularly when diagnosing subtle pathologies that may not present with overt symptoms but can significantly impact long-term joint health.
Anatomical Boundaries and Structural Components
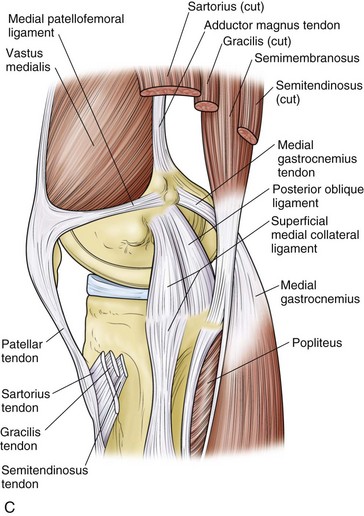
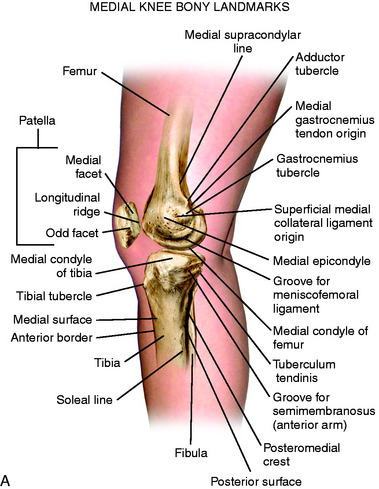
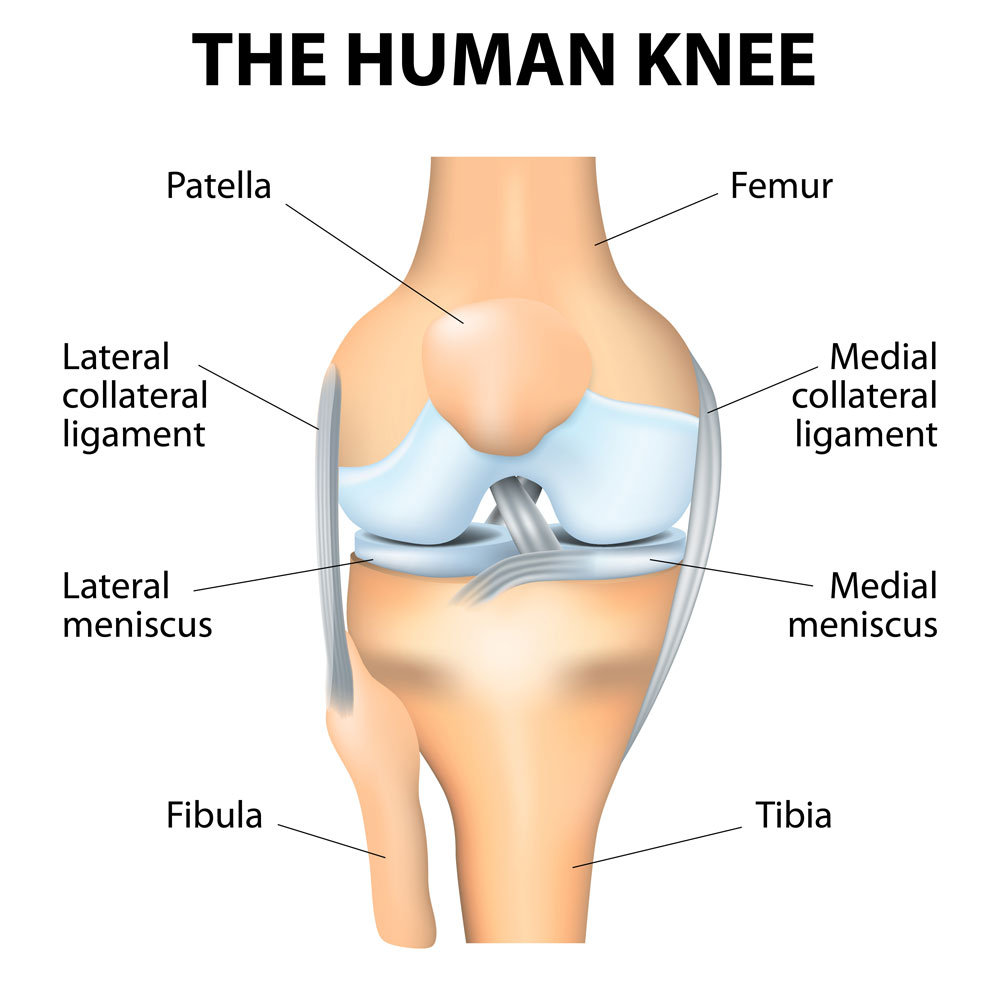
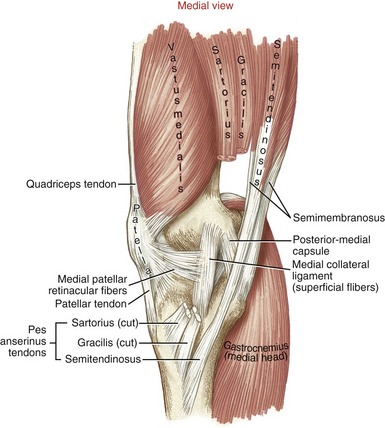
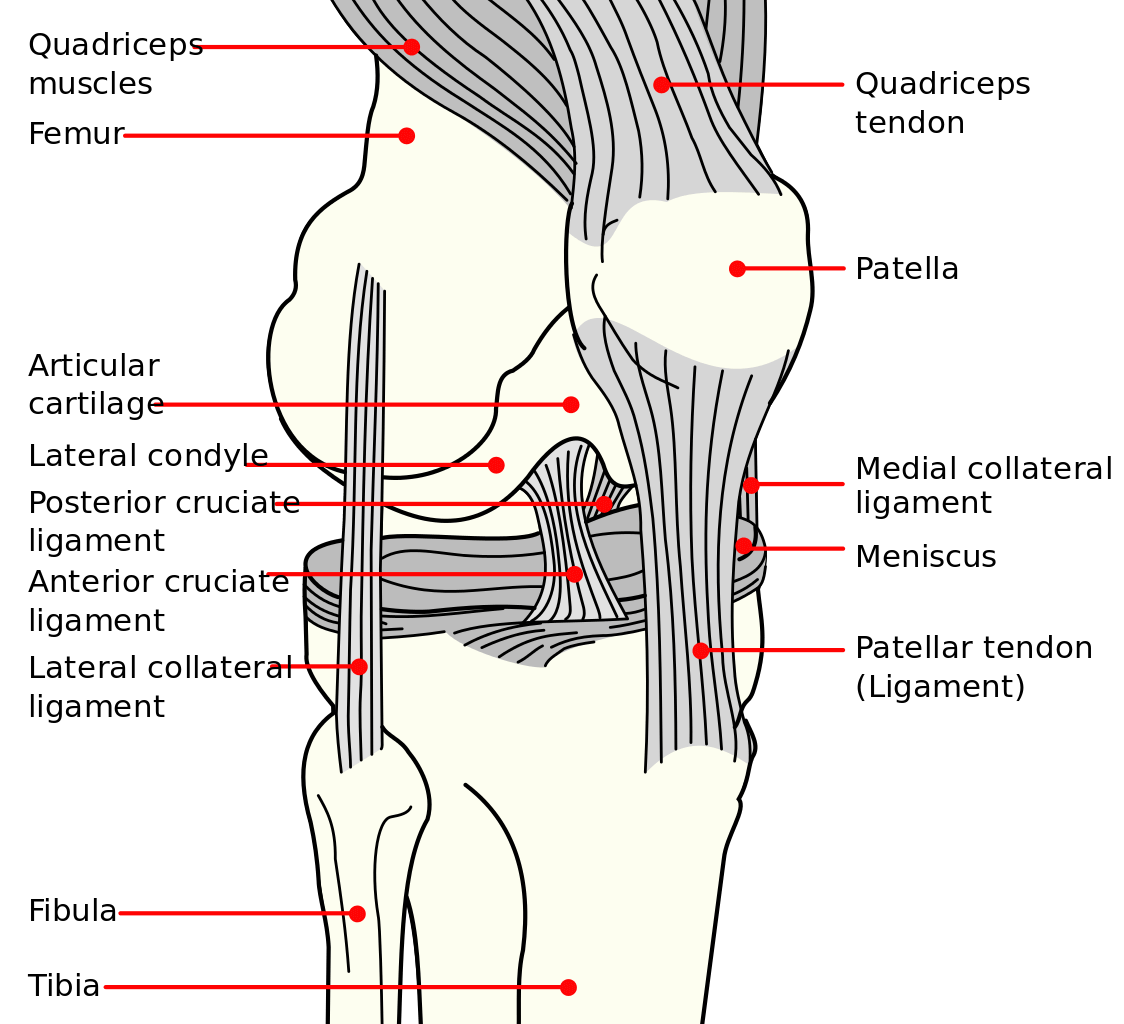
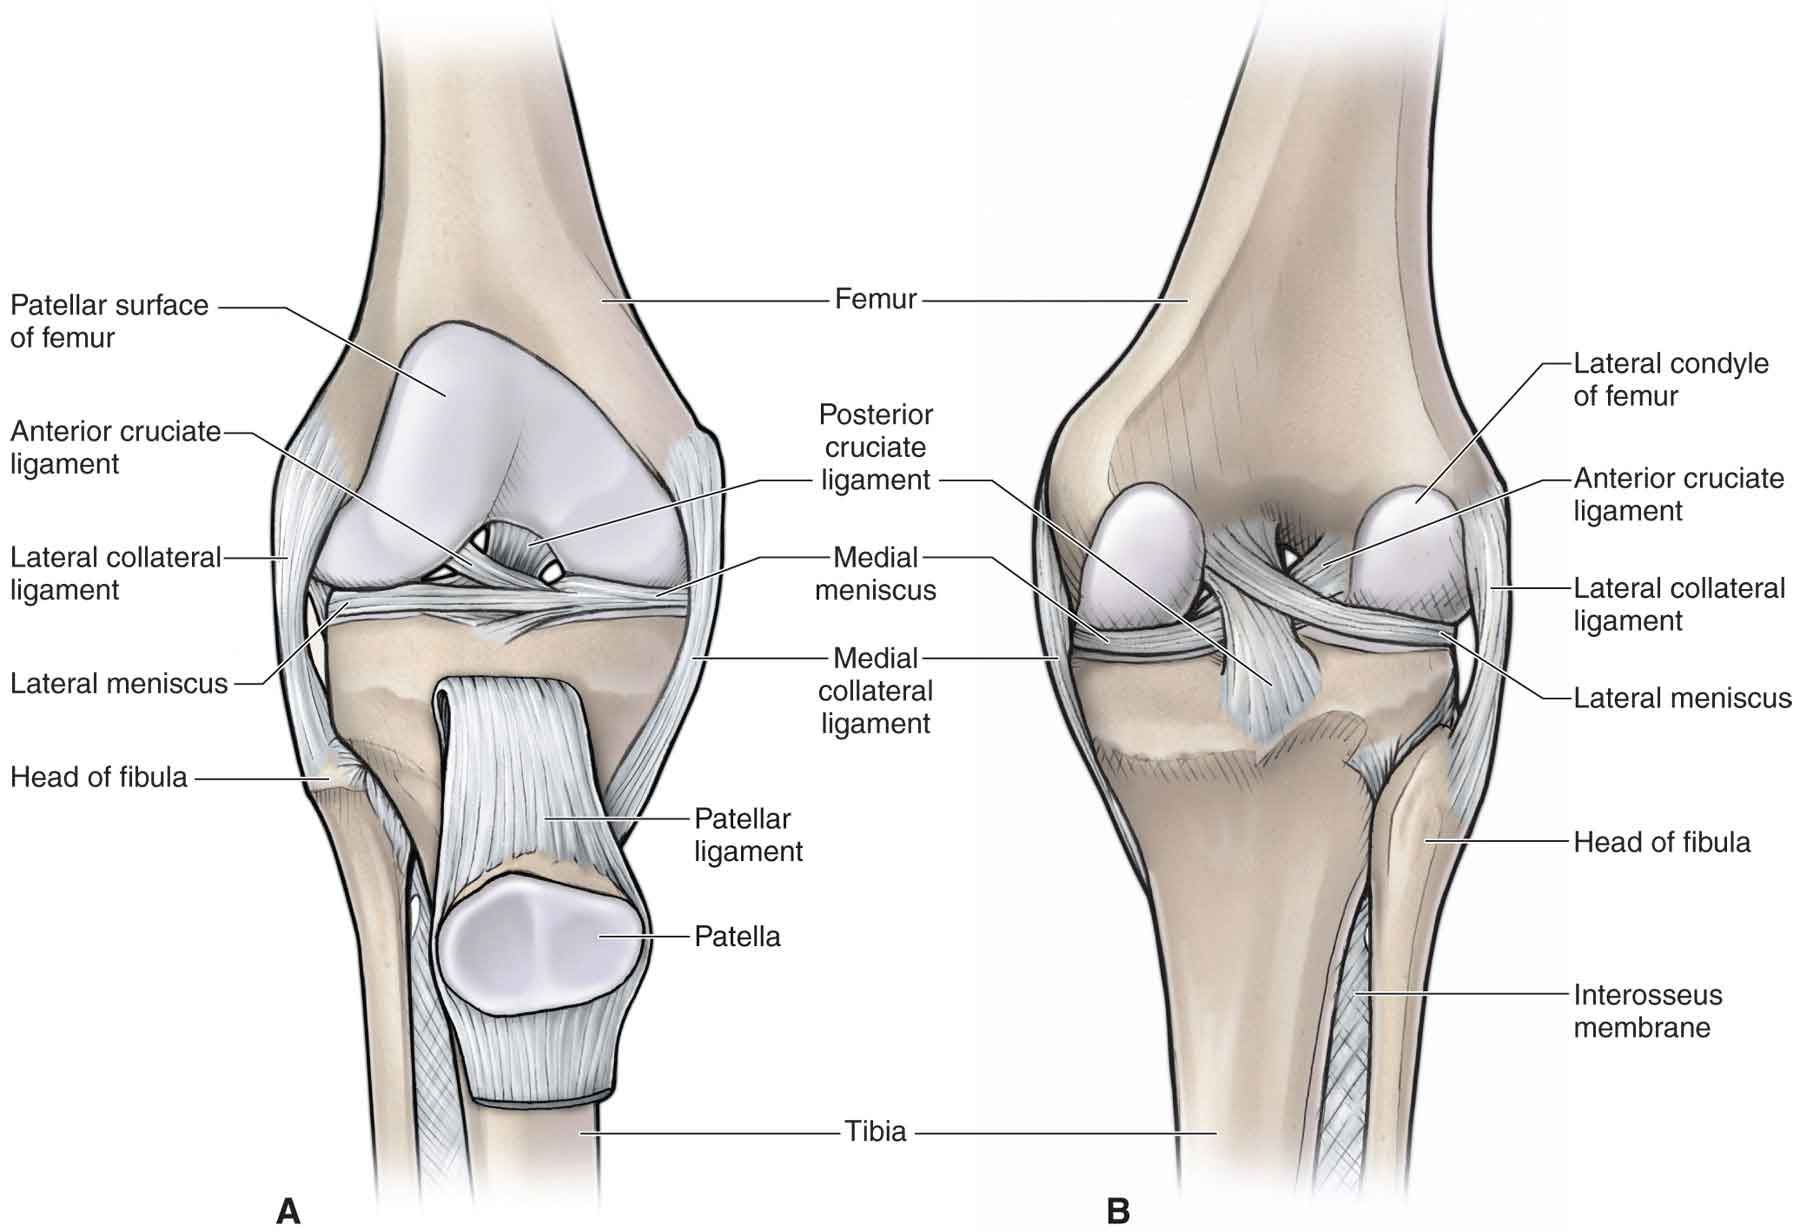
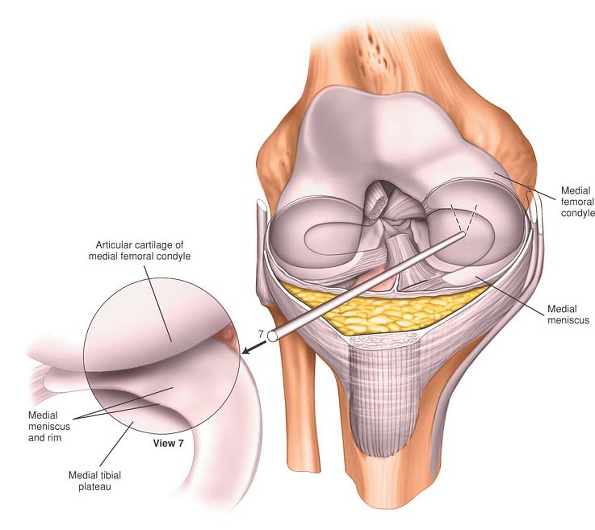
The medial gutter is located along the inner aspect of the knee joint, nestled between the medial femoral condyle and the tibial plateau. It is lined by synovial membrane and contains several key structures: the medial meniscus, the medial collateral ligament (MCL), the semimembranosus tendon, and portions of the pes anserinus. The medial meniscus, a C-shaped fibrocartilaginous structure, acts as a shock absorber and stabilizer, distributing compressive forces during weight-bearing activities. Its attachment to the deep layer of the MCL creates a functional unit that resists valgus stress and rotational forces. Disruption in this region—whether from acute trauma or degenerative changes—can lead to altered joint mechanics and early-onset osteoarthritis.
Synovial Tissue and the Medial Plica
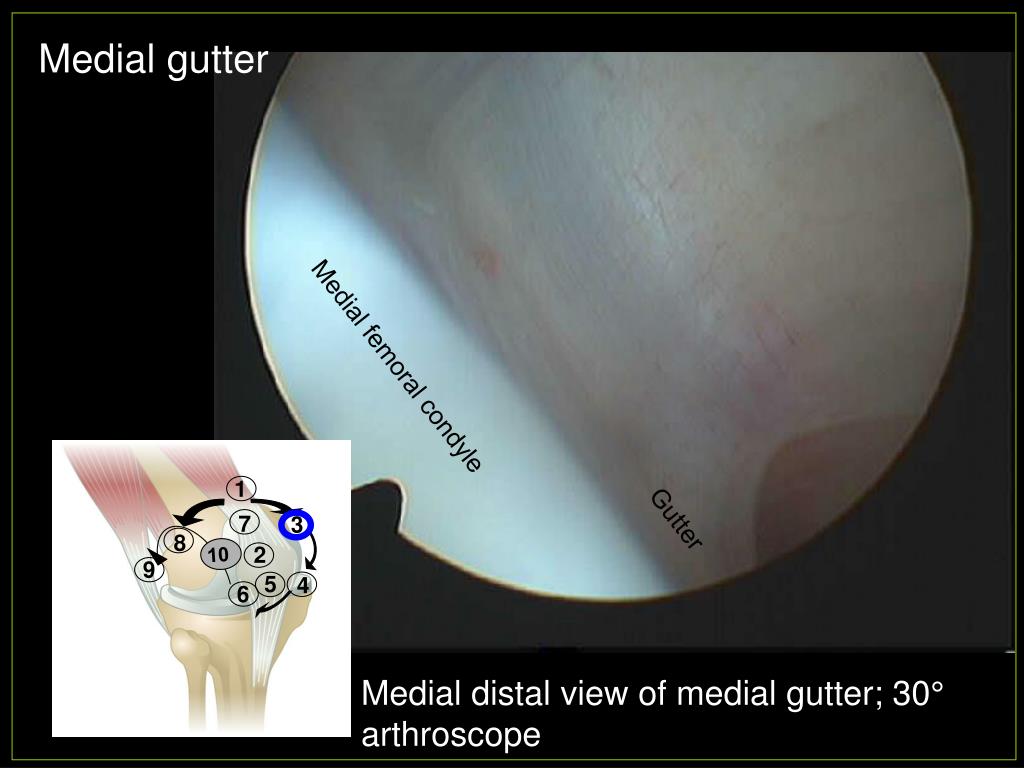
Within the medial gutter lies the medial plica, a remnant of embryonic development that persists in up to 60% of the population. While often asymptomatic, an inflamed or thickened medial plica can cause anterior knee pain, clicking, or a sensation of catching—symptoms frequently misattributed to meniscal tears. Accurate diagnosis requires a nuanced understanding of this structure’s variability and its interaction with adjacent tissues. Imaging modalities such as MRI or diagnostic arthroscopy are essential tools for differentiating plica syndrome from other intra-articular pathologies.
Clinical Relevance in Injury and Degeneration
Injuries to the medial gutter are common in sports involving sudden changes in direction or direct impact to the lateral knee, which places excessive valgus stress on the medial structures. A grade II MCL sprain, for instance, involves partial tearing of the ligament and may be accompanied by concurrent meniscal damage due to the intimate anatomical relationship between these structures. Chronic overuse can lead to medial compartment osteoarthritis, where cartilage wear in the gutter accelerates joint space narrowing and pain. Early intervention—including bracing, physical therapy, and activity modification—can mitigate progression and preserve function.
Diagnostic Imaging and Assessment
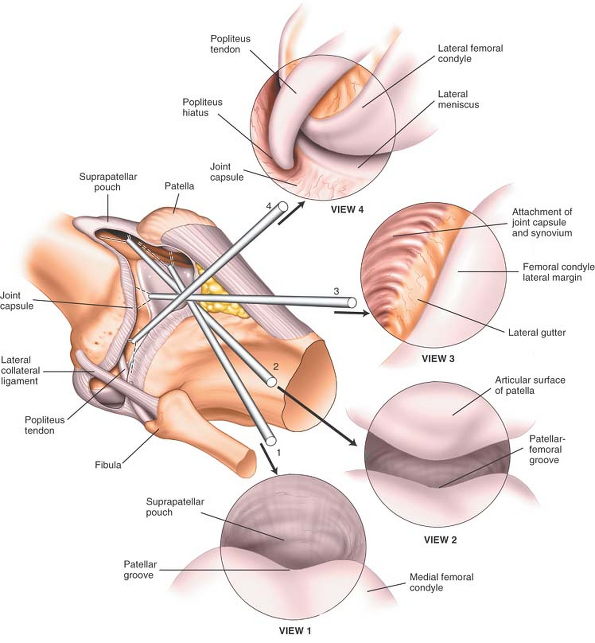
Accurate assessment of the medial gutter demands a multimodal approach. MRI remains the gold standard for visualizing soft tissue integrity, particularly for detecting subtle meniscal tears or ligamentous laxity. Ultrasound offers dynamic evaluation of the MCL and pes anserinus, while weight-bearing radiographs reveal joint space changes indicative of cartilage loss. Clinicians must correlate imaging findings with physical examination maneuvers—such as the valgus stress test or McMurray’s test—to form a comprehensive diagnostic picture.
Rehabilitation and Preventive Strategies
Rehabilitation following medial gutter injury focuses on restoring neuromuscular control, strengthening the vastus medialis oblique (VMO), and improving proprioception. Eccentric exercises targeting the hamstrings and quadriceps help stabilize the joint and reduce re-injury risk. Preventive programs emphasizing proper biomechanics during cutting and landing maneuvers are especially valuable in athletic populations. Long-term joint health hinges on early recognition of subtle dysfunction before irreversible structural damage occurs.

Understanding the medial gutter’s intricate anatomy empowers both patients and providers to address knee issues with precision. Whether managing acute trauma or chronic degeneration, a deep appreciation of this region’s complexity ensures more effective treatment outcomes and sustained mobility.