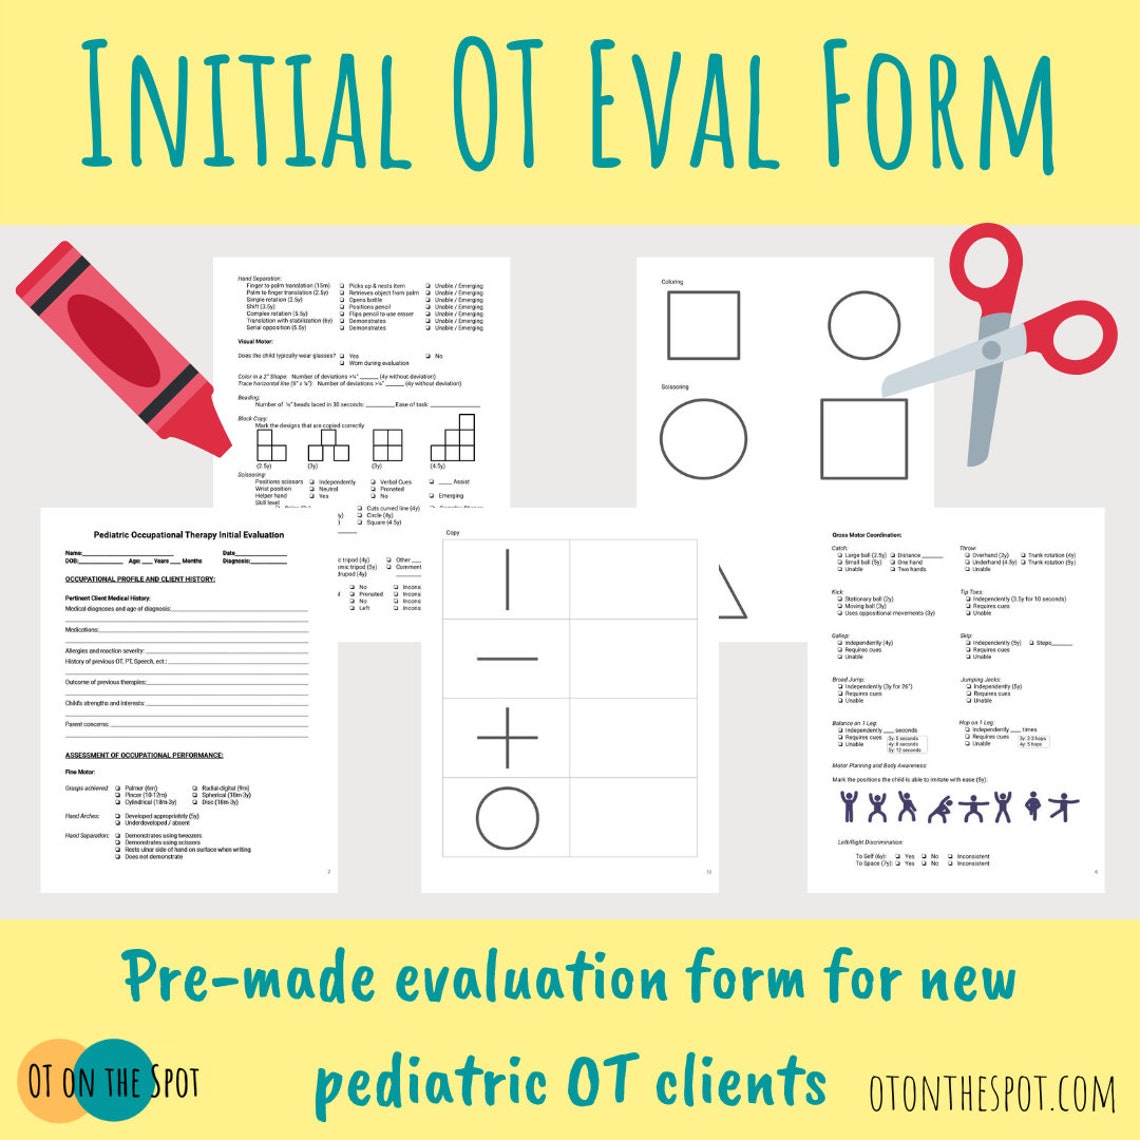
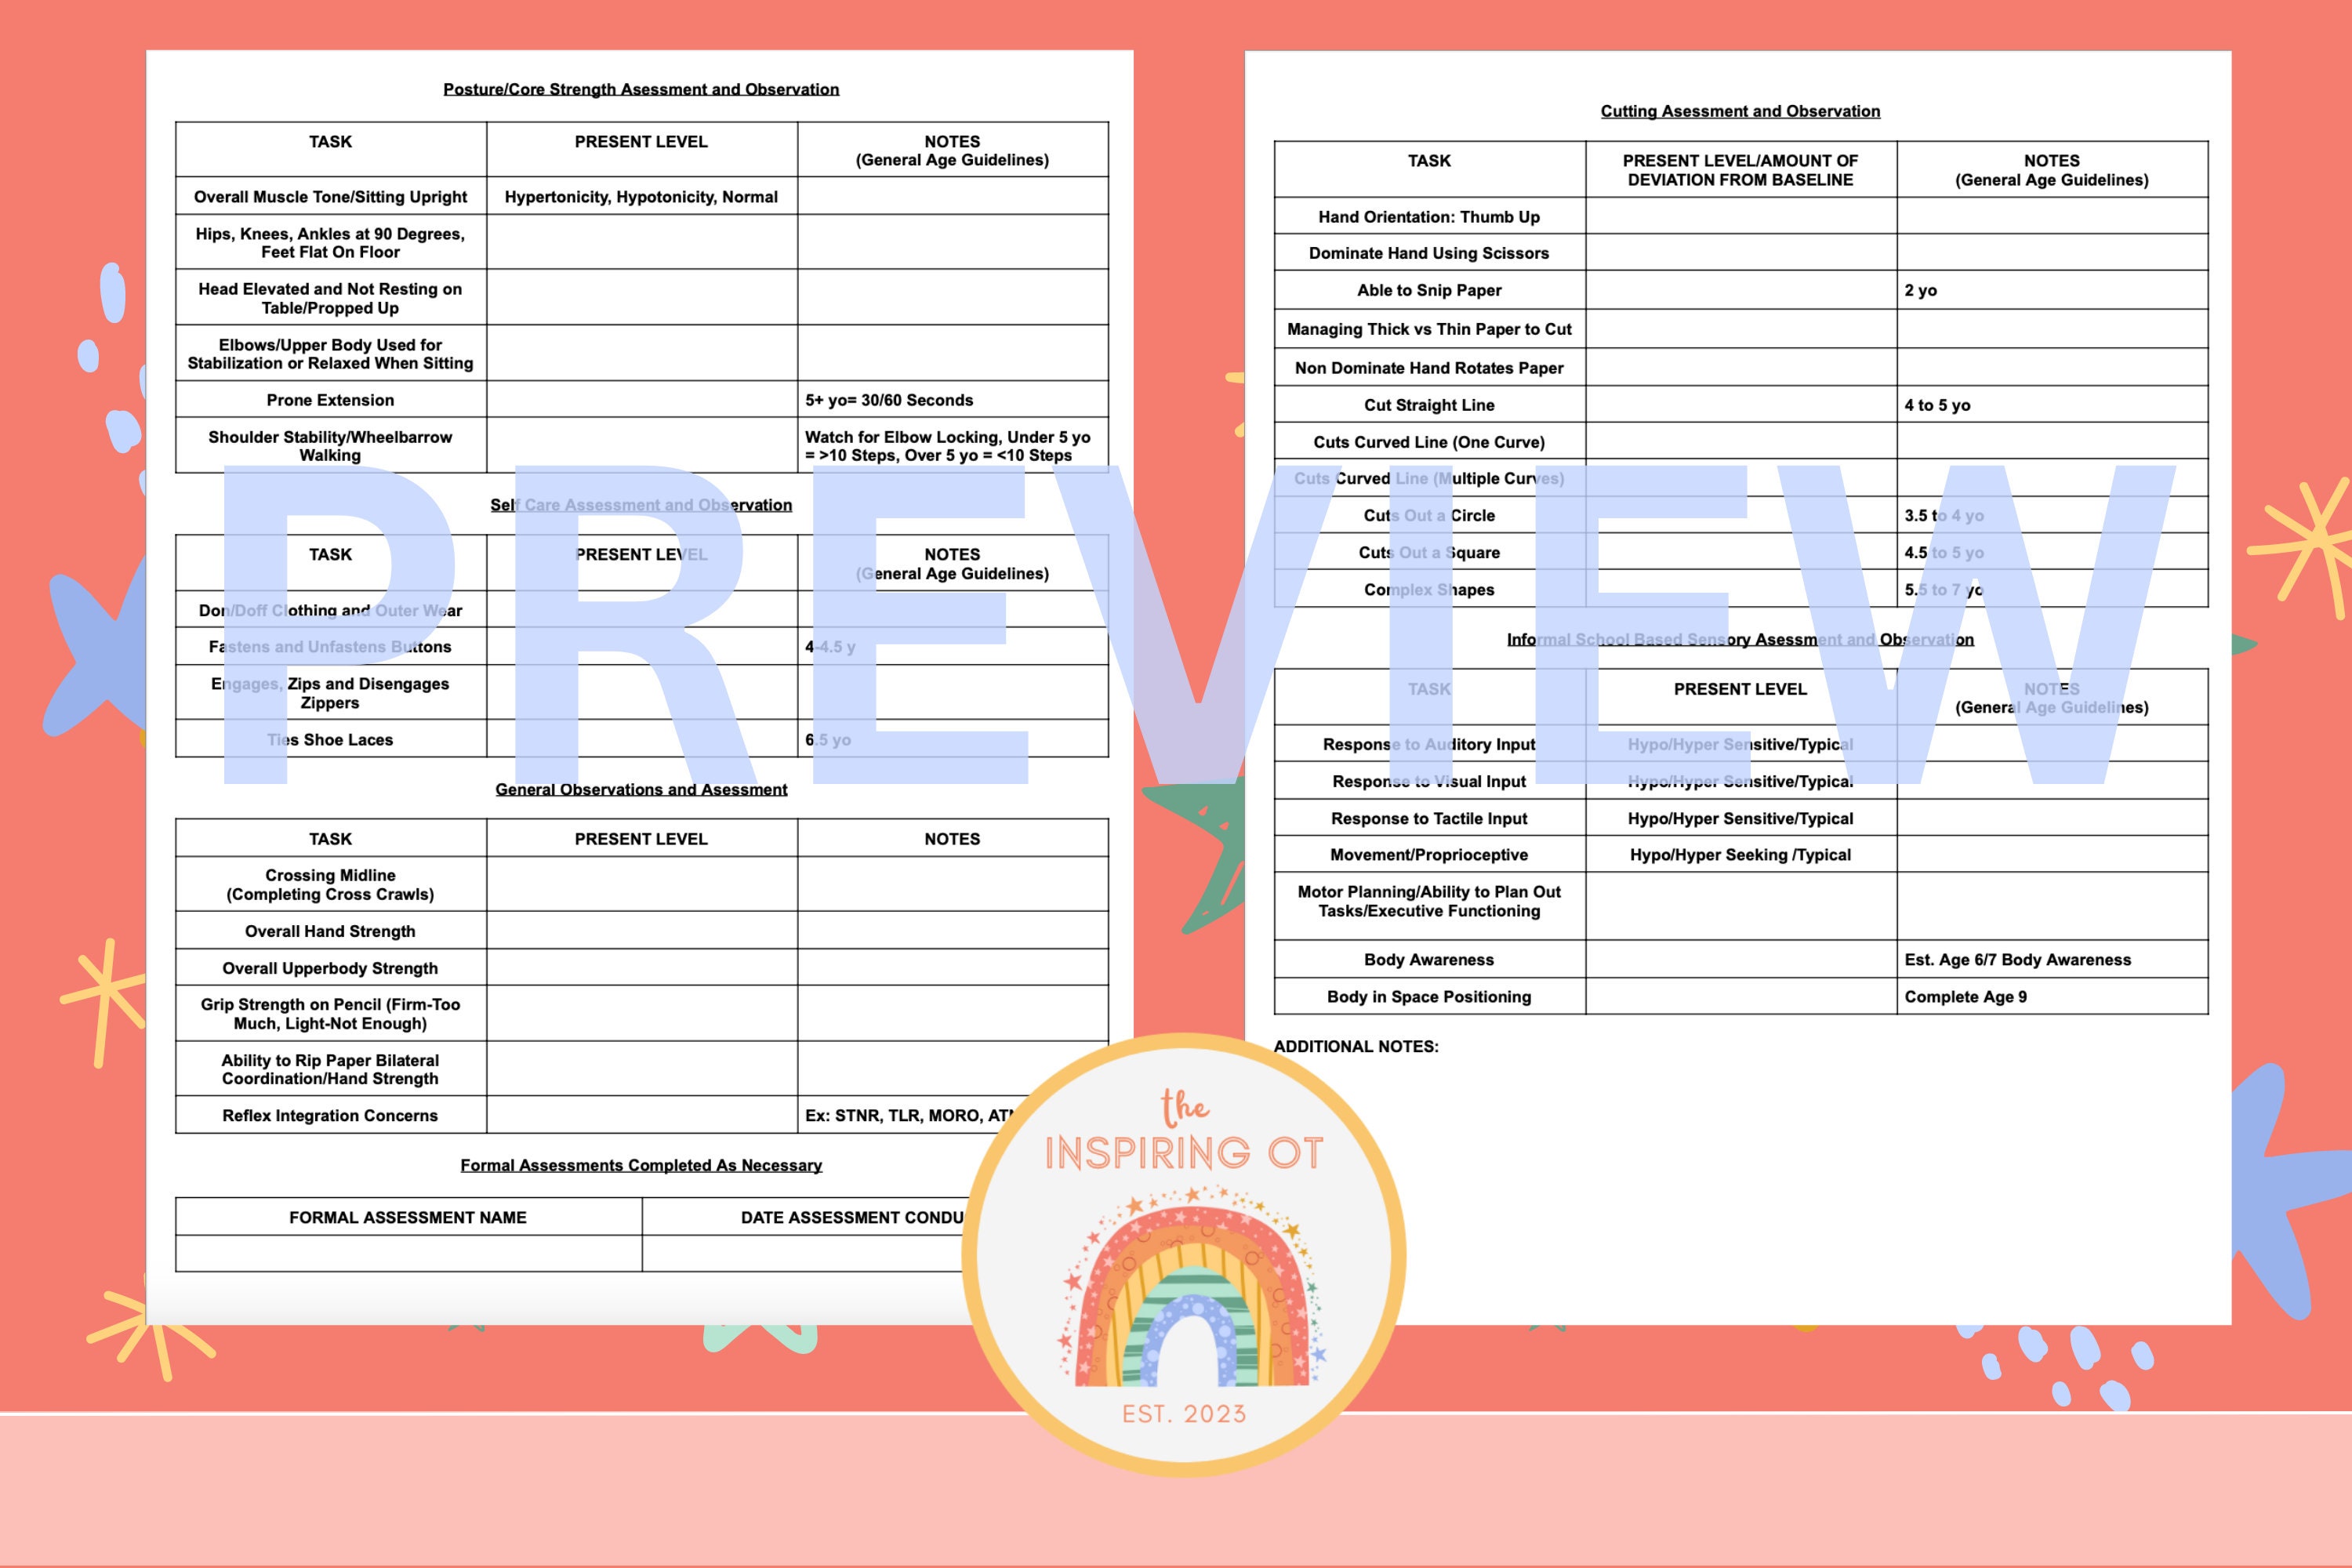
Pediatric occupational therapy assessment is a critical first step in identifying a child’s strengths, challenges, and developmental needs. Unlike standardized testing alone, a comprehensive evaluation integrates clinical observation, caregiver input, and evidence-based tools to build a holistic picture of how a child functions across daily activities—from self-care and play to school participation. The format of this assessment varies by setting and purpose, but its core goal remains consistent: to guide meaningful, individualized intervention.
Core Components of a Pediatric OT Assessment Format
A well-structured pediatric occupational therapy assessment typically includes several key elements. These components ensure that therapists gather both quantitative data and qualitative insights. Below are the foundational pillars most clinicians rely on:
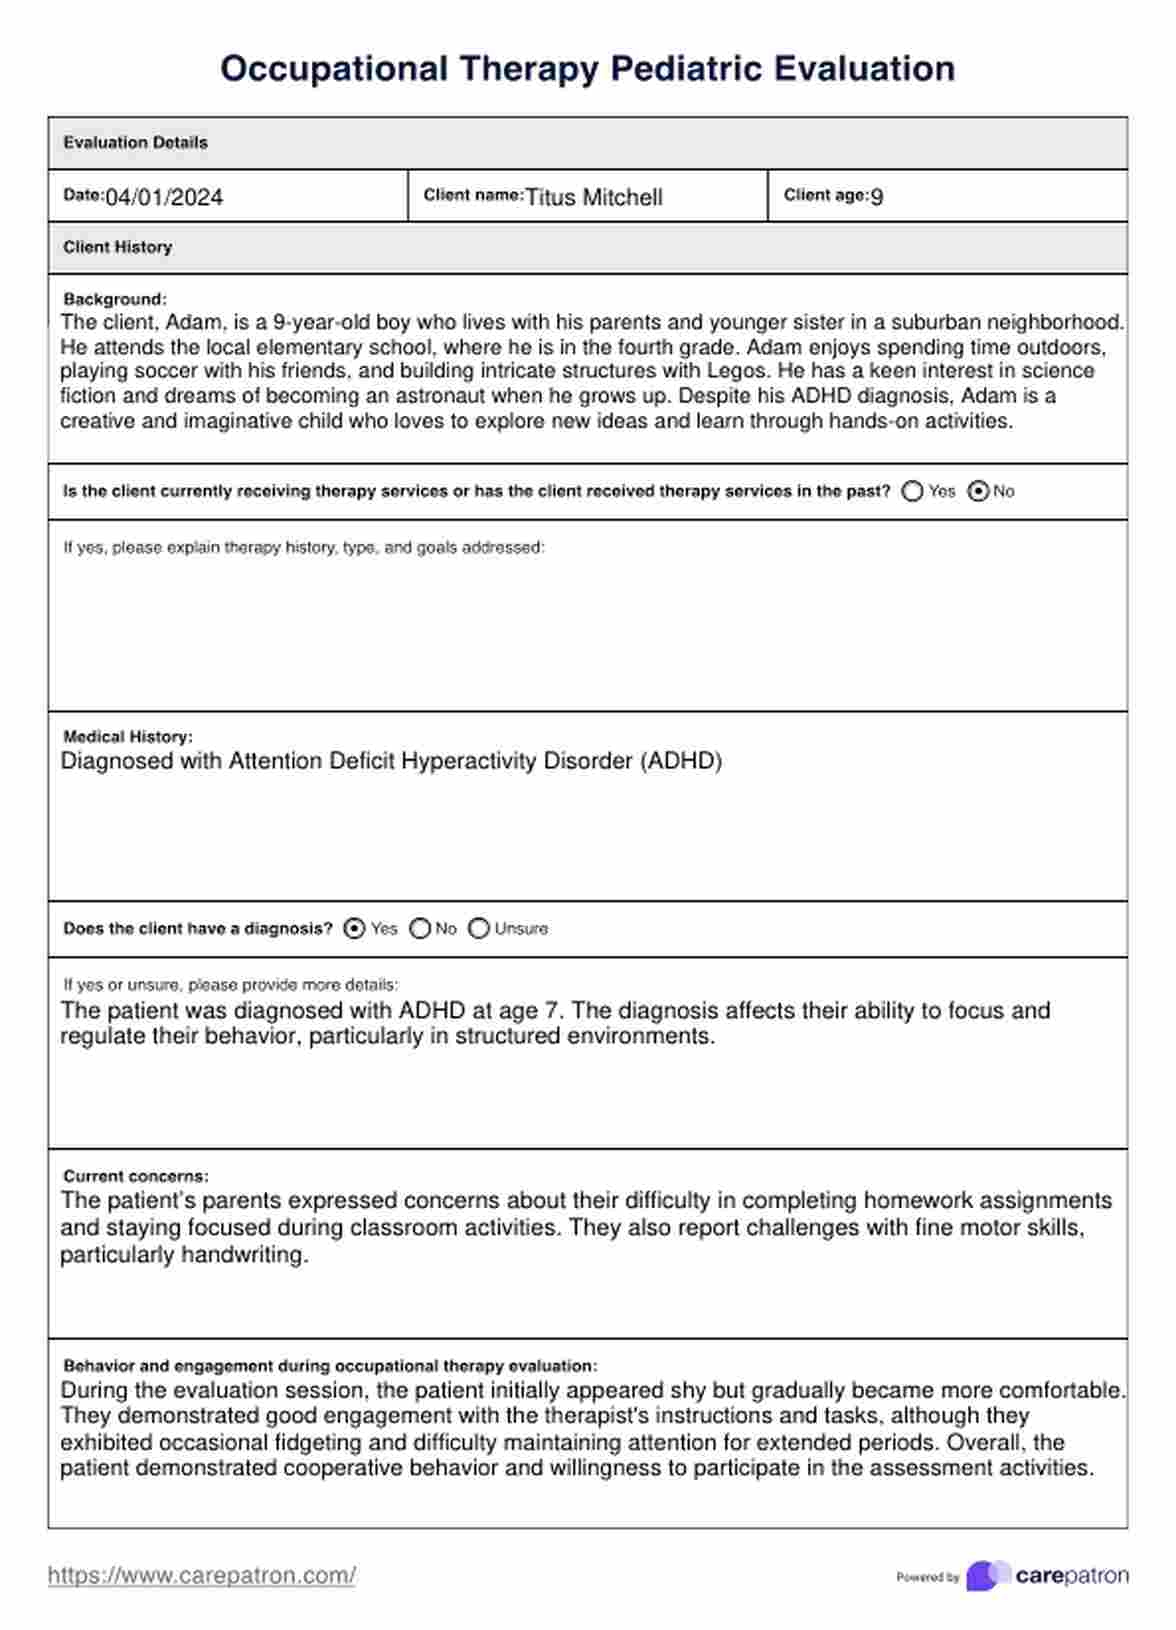
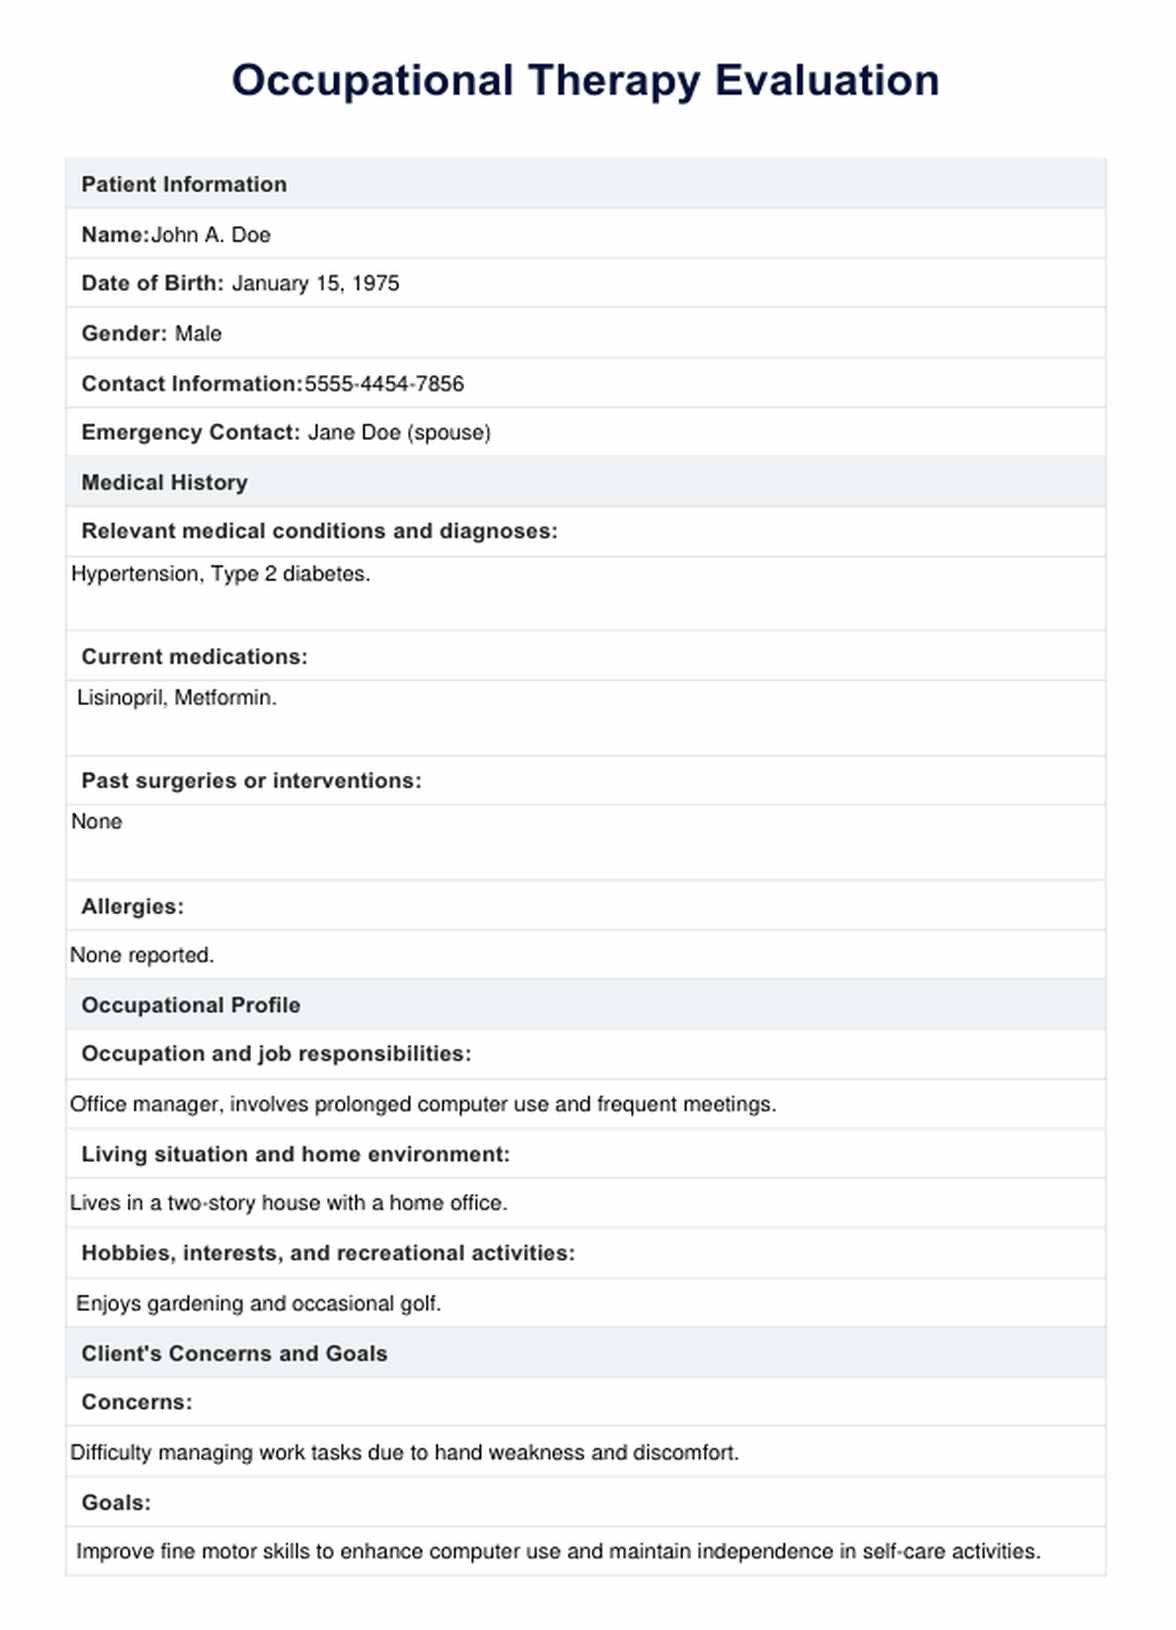
- Referral and Background Information: This includes medical history, developmental milestones, educational status, and reasons for referral (e.g., fine motor delays, sensory processing concerns, or handwriting difficulties).
- Caregiver and Teacher Interviews: Structured or semi-structured conversations provide context about the child’s behavior, routines, and challenges in natural environments.
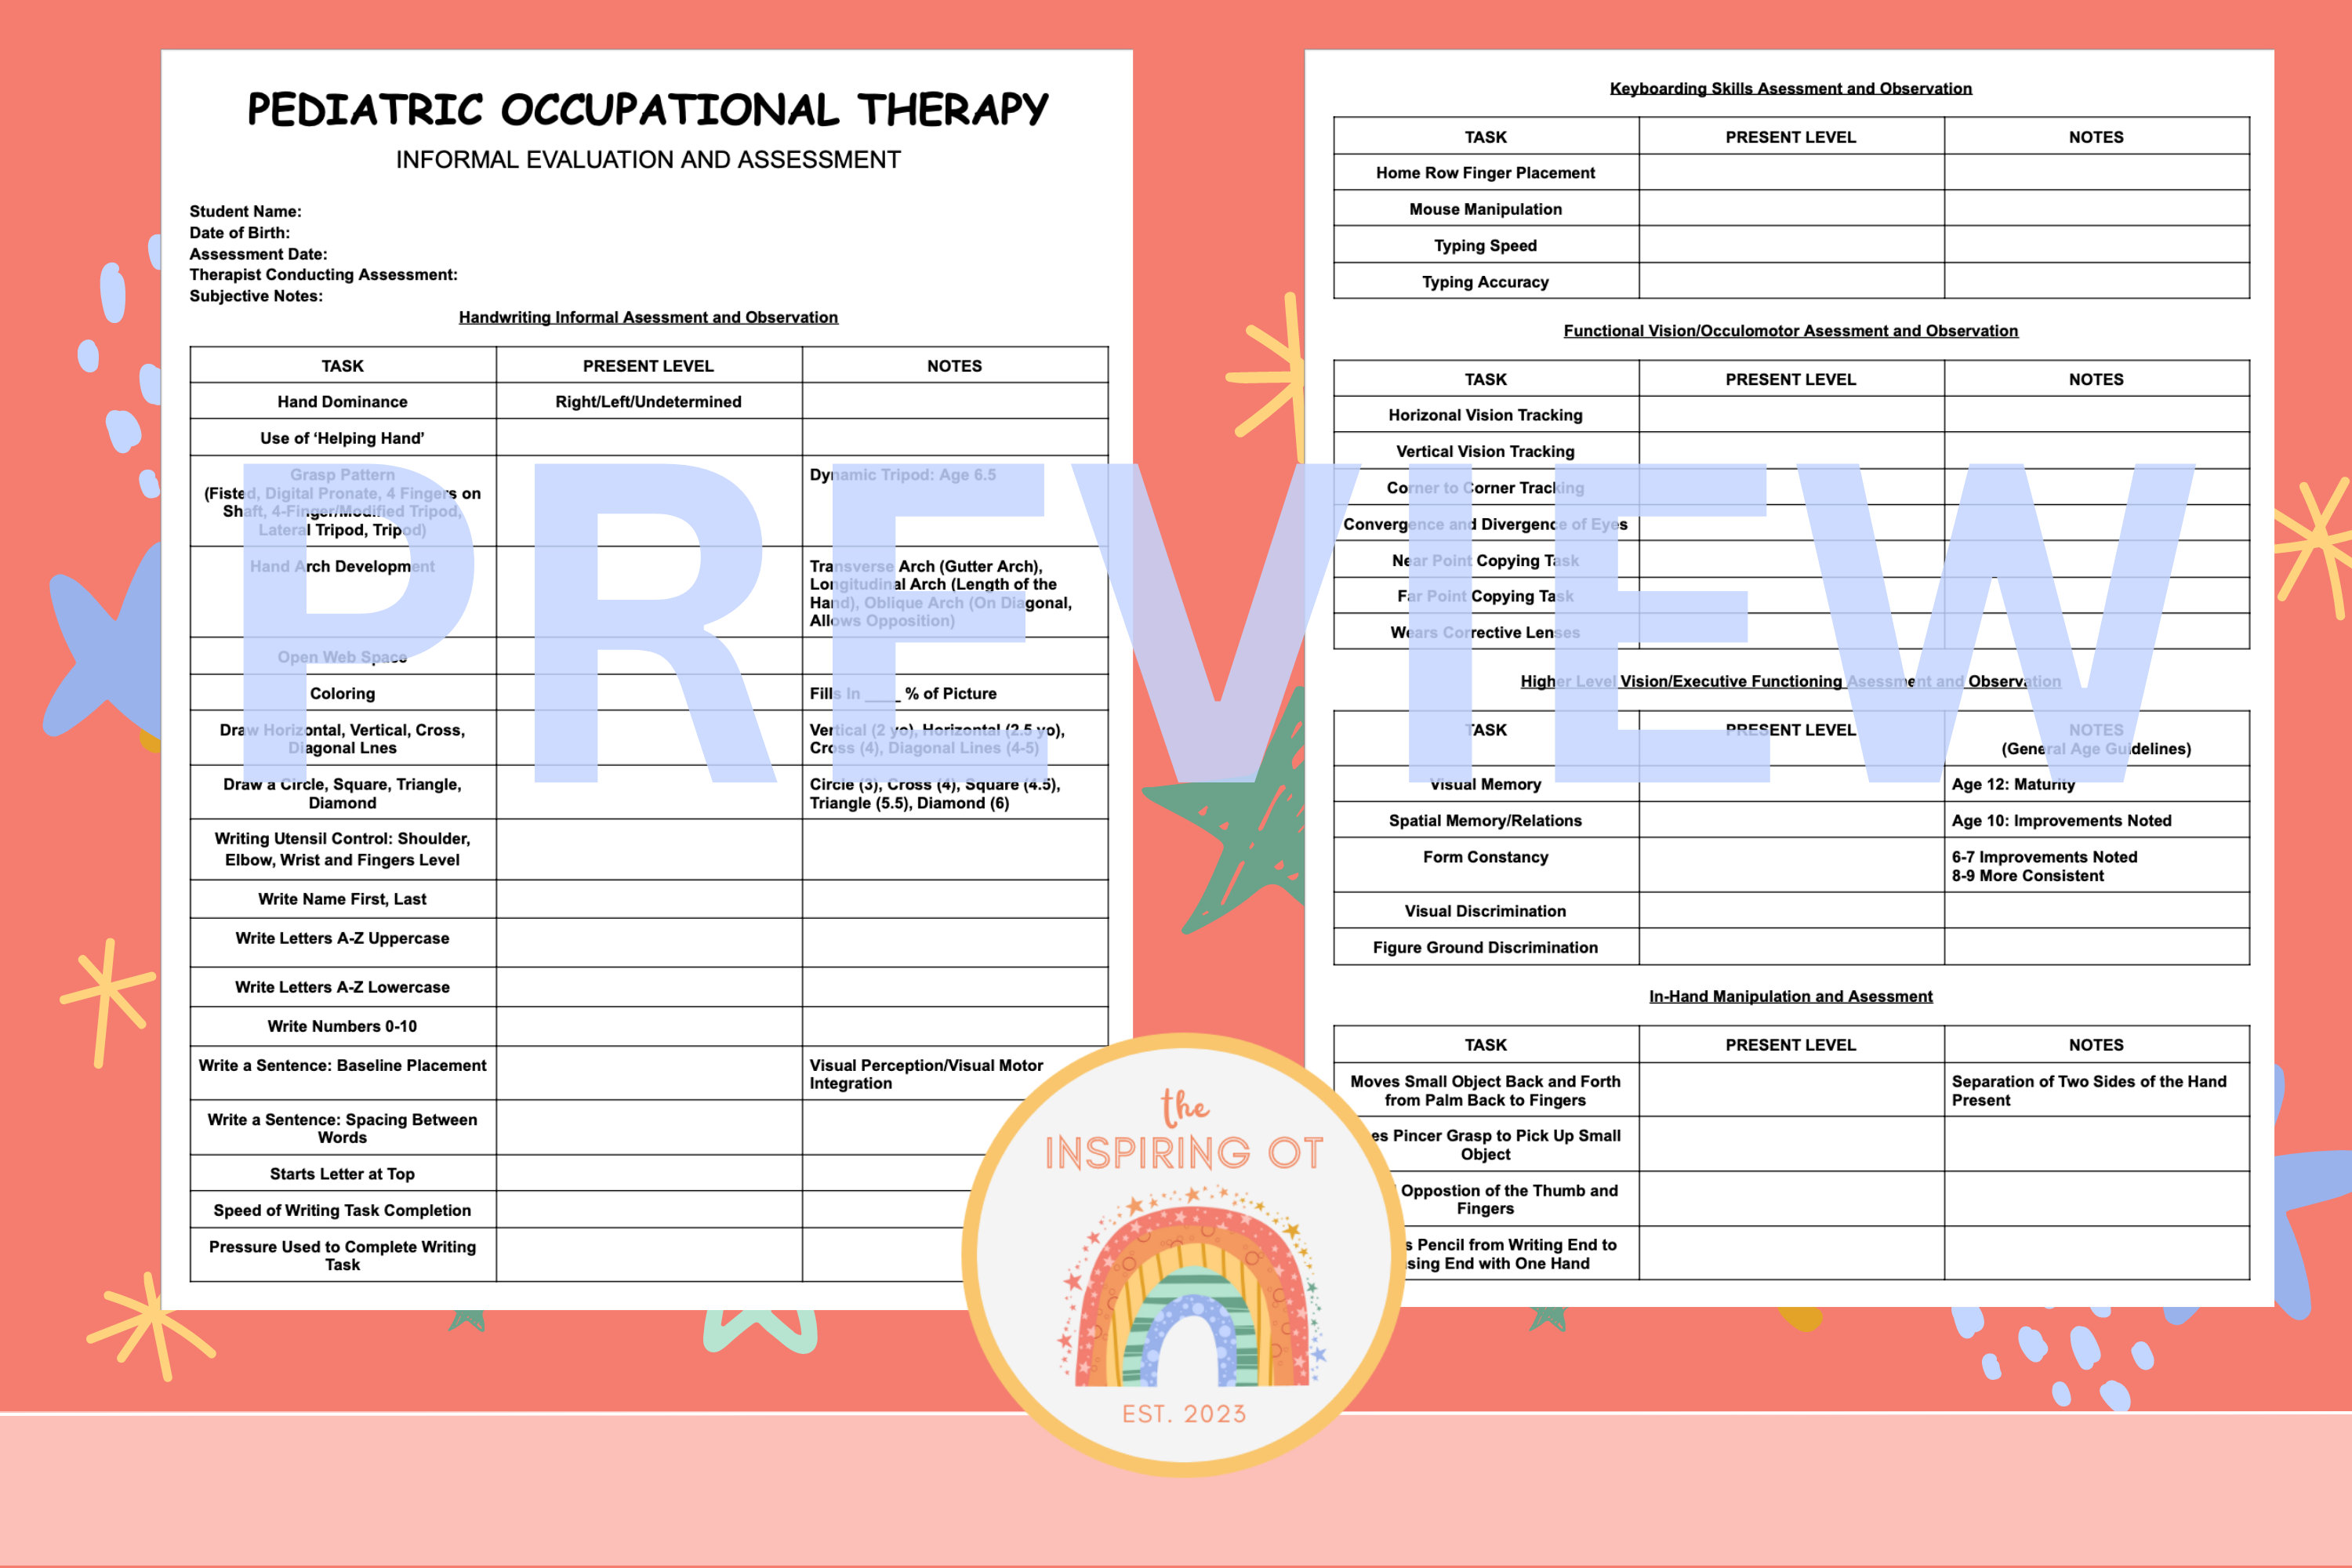
- Standardized Assessments: Validated tools such as the Peabody Developmental Motor Scales (PDMS-2), Beery-Buktenica Developmental Test of Visual-Motor Integration (Beery VMI), or Sensory Profile help benchmark performance against age norms.
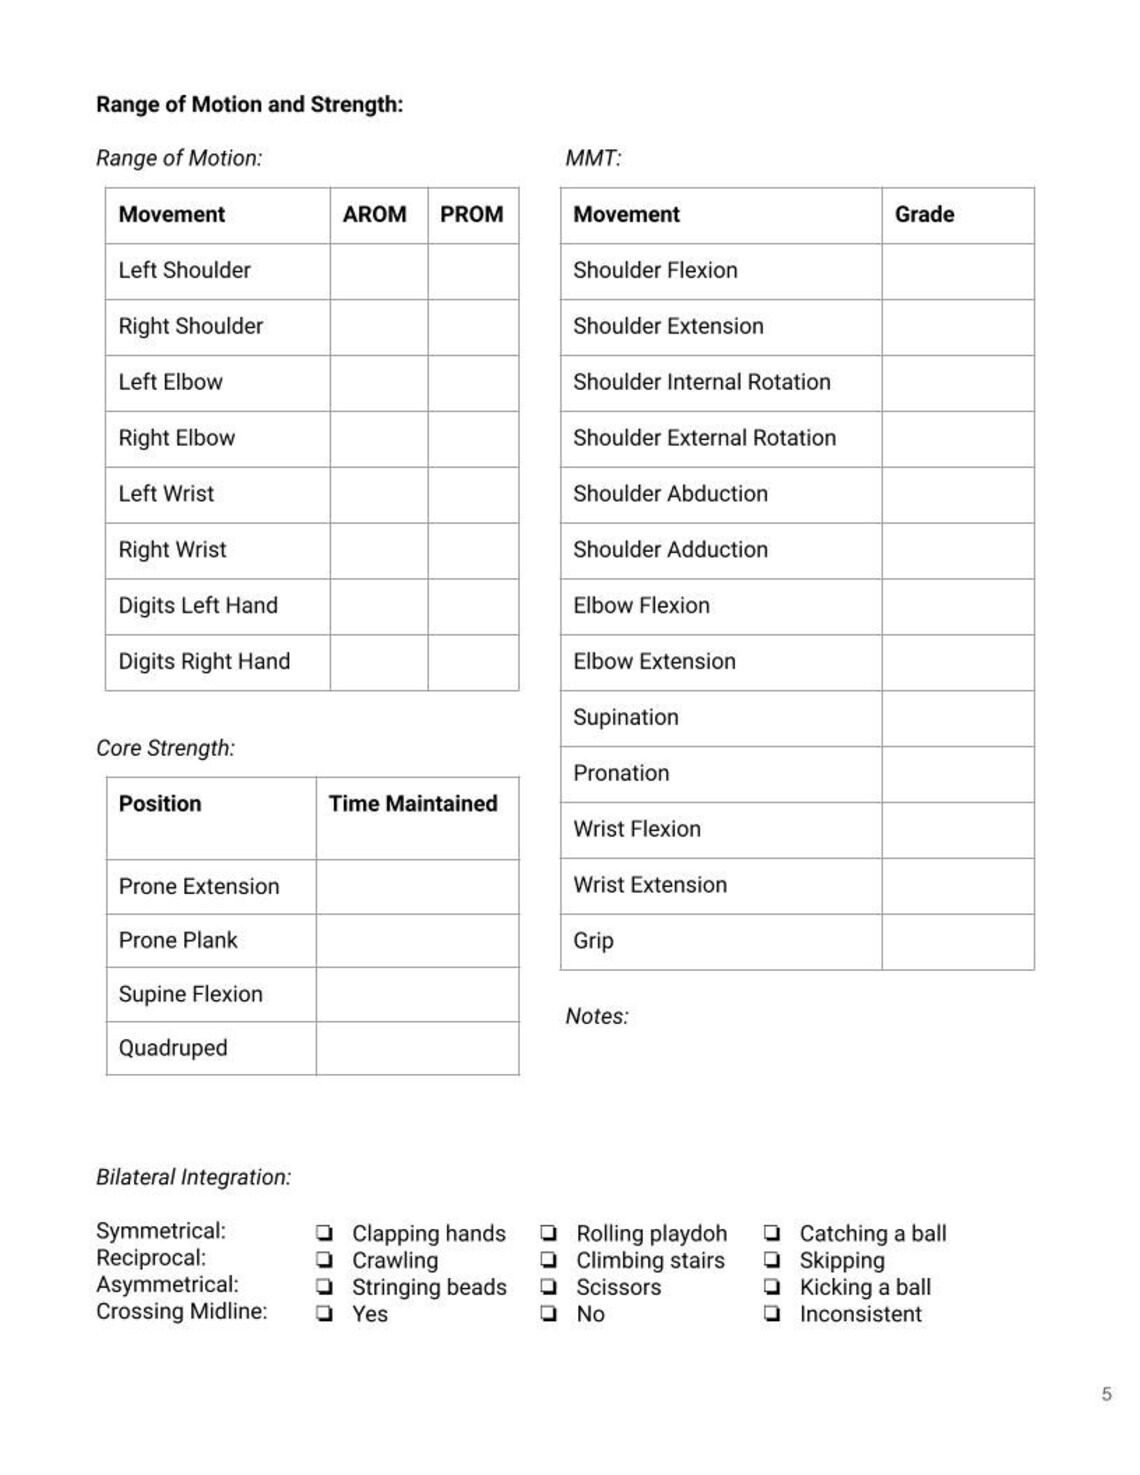
- Clinical Observations: Therapists observe posture, coordination, attention, social interaction, and task completion during play or functional activities.
- Functional Performance Analysis: Direct assessment of how the child performs real-world tasks like dressing, writing, or using utensils.
Commonly Used Standardized Tools in Pediatric OT Assessments
Selecting the right assessment tool depends on the child’s age, suspected areas of difficulty, and the therapist’s clinical judgment. Here’s a quick reference table outlining widely used instruments:

| Assessment Tool | Primary Focus Area | Age Range |
|---|---|---|
| Peabody Developmental Motor Scales (PDMS-2) | Gross and fine motor skills | Birth–5 years |
| Beery-Buktenica Developmental Test of Visual-Motor Integration (Beery VMI) | Visual perception and motor coordination | 2–100 years |
| Sensory Profile 2 | Sensory processing patterns | Birth–14 years |
| Bruininks-Oseretsky Test of Motor Proficiency (BOT-2) | Motor proficiency | 4–21 years |
Why Standardization Matters—but Isn’t Everything
While standardized tests offer objective metrics, they don’t capture the full story. A child might score within normal limits on a pencil-and-paper task but struggle significantly during classroom writing due to poor posture, low endurance, or anxiety. That’s why skilled therapists pair test scores with dynamic assessment—observing how a child responds to cues, adapts strategies, or engages with peers. This dual approach ensures recommendations are grounded in both data and real-life function.
Structuring the Assessment Report
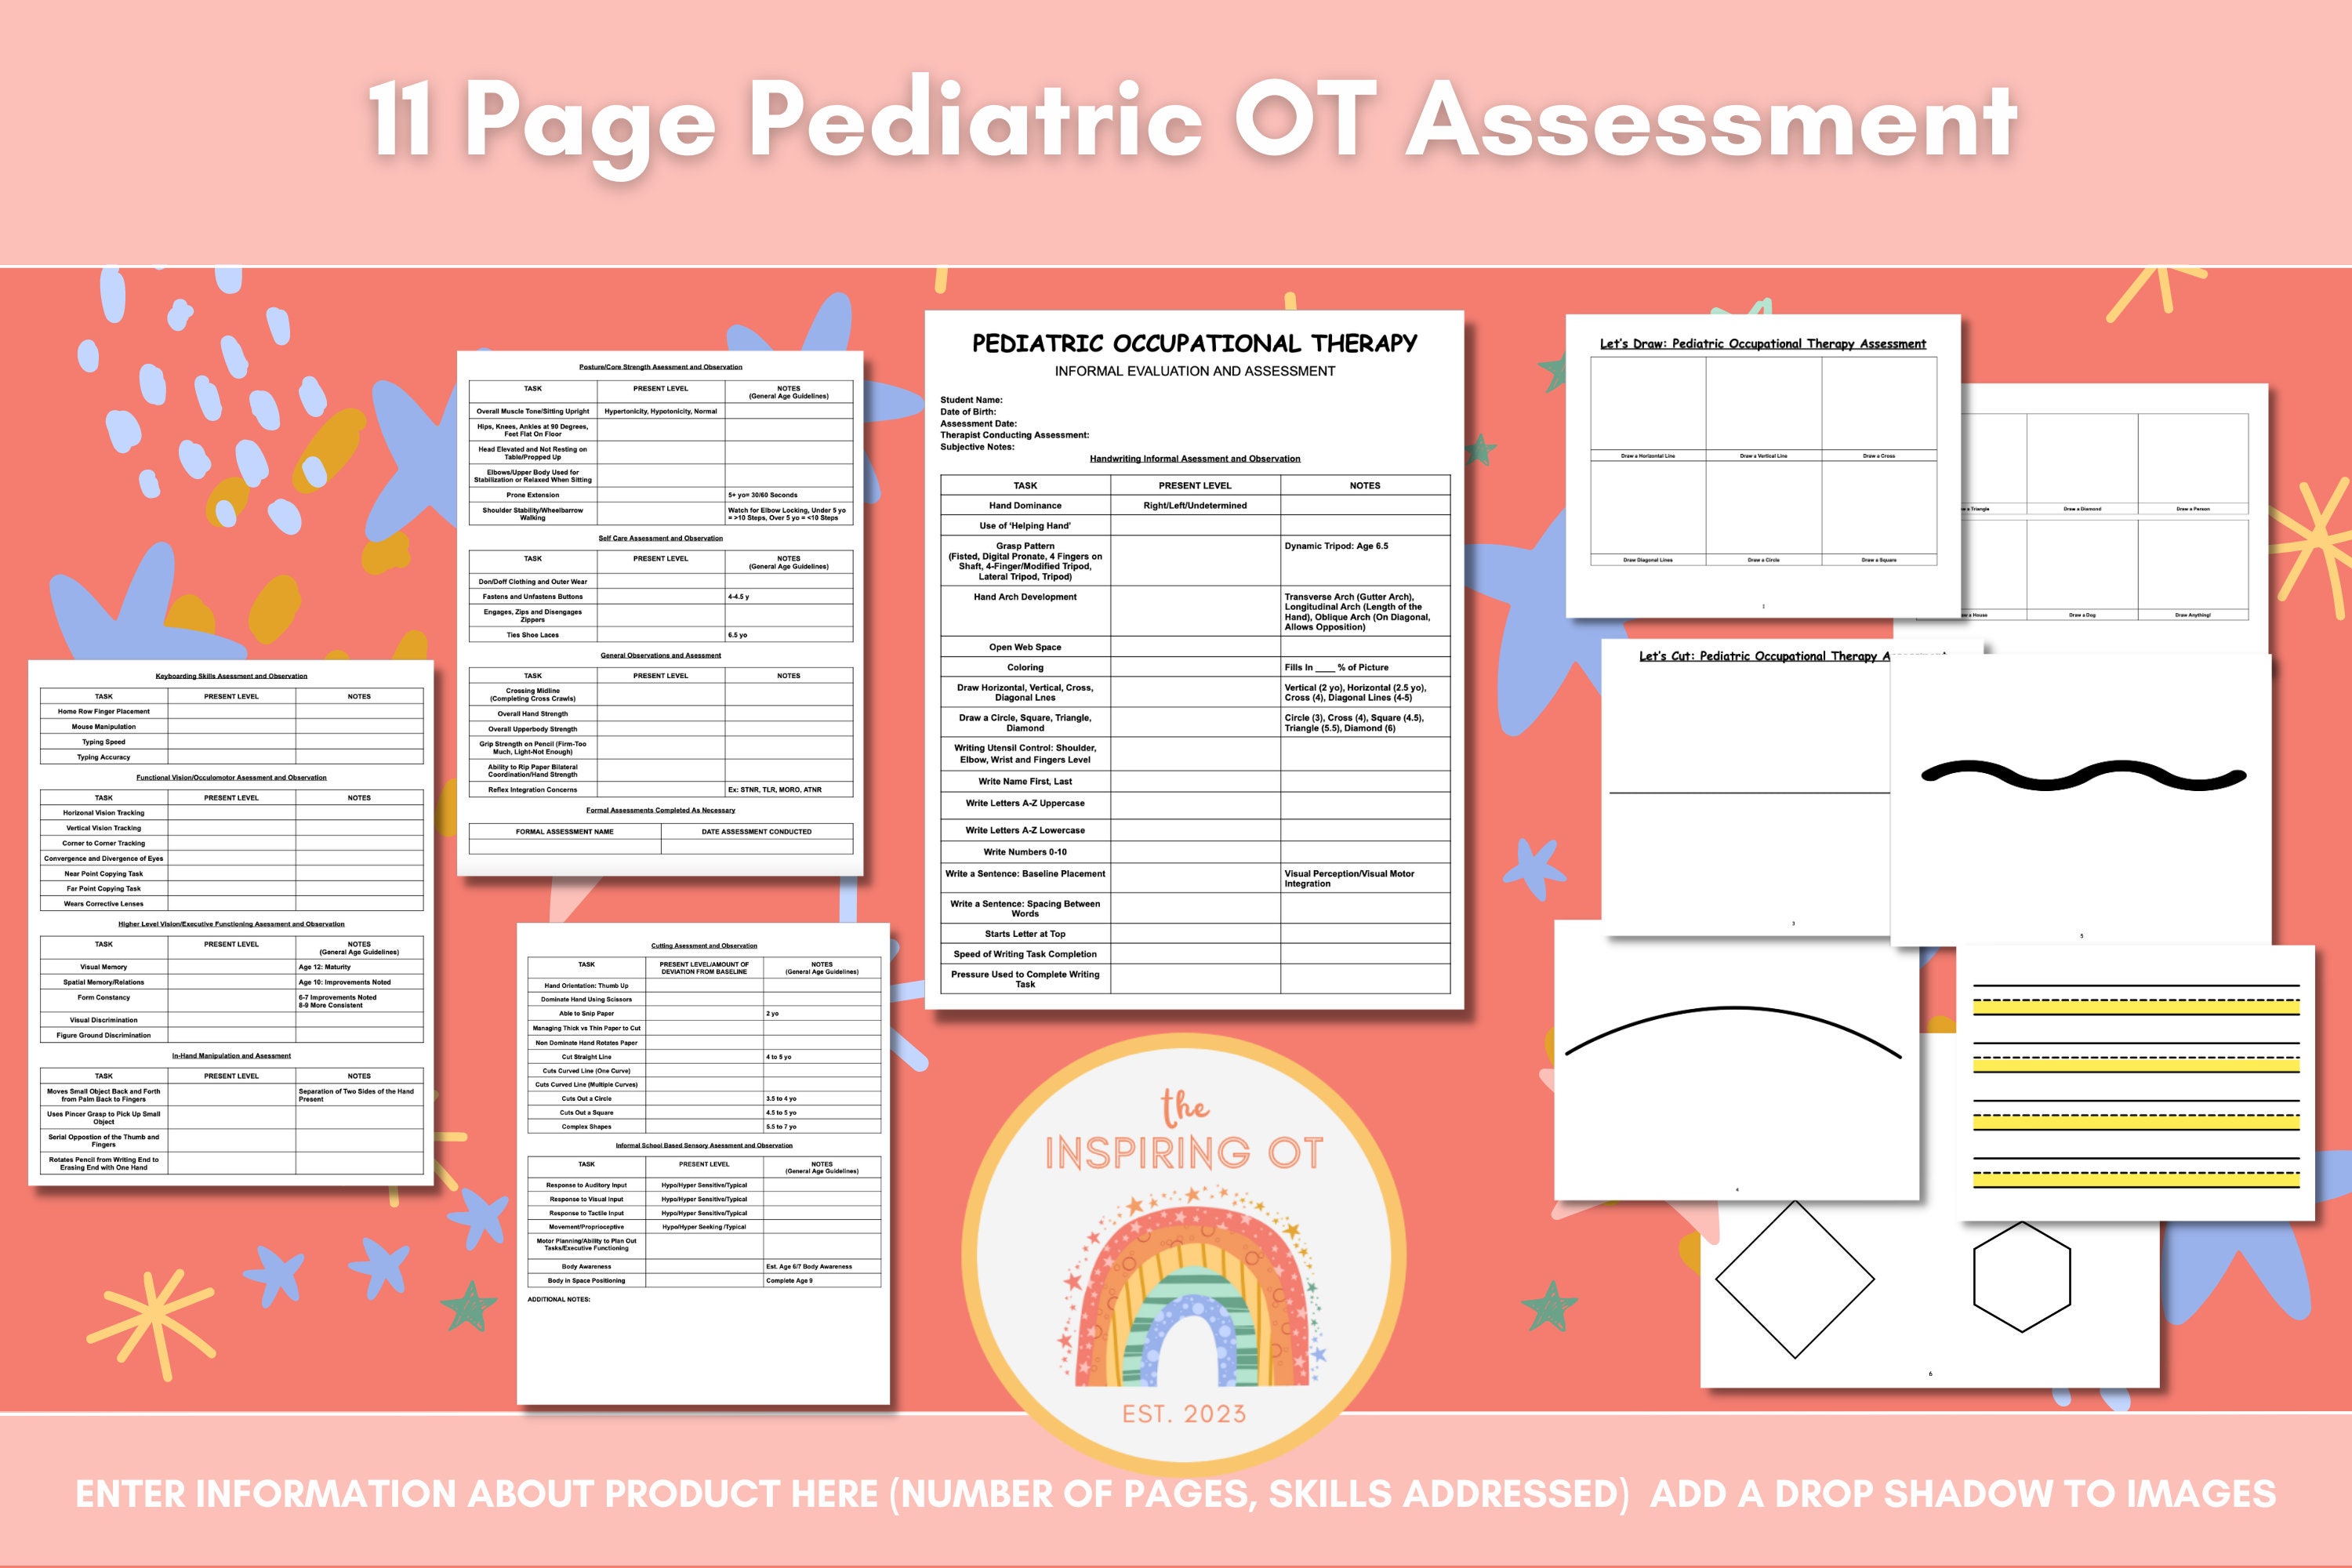
After gathering all information, the therapist compiles findings into a clear, actionable report. A strong pediatric OT assessment format in documentation includes:
- Identifying Information: Child’s name, date of birth, date of evaluation, and referring provider.
- Reason for Referral: Concise statement of the concern (e.g., “Difficulty with buttoning shirts and using scissors”).
- Assessment Methods: List of tools used and observations made.
- Findings: Summary of performance across domains (motor, sensory, cognitive, social-emotional).
- Clinical Impressions: Interpretation of results in context of daily functioning.
- Recommendations: Specific, measurable goals and intervention strategies tailored to the child’s needs.
Adapting the Format Across Settings
The assessment format shifts depending on whether the therapist works in a school, clinic, hospital, or home-based program. In schools, evaluations often align with IDEA guidelines and focus on educational impact. In medical settings, they may emphasize neurological or orthopedic factors. Regardless of context, the best formats remain family-centered—ensuring parents understand results and feel empowered to support their child’s progress.
Final Thoughts on Effective Assessment Practices
A pediatric occupational therapy assessment isn’t just a checklist—it’s a collaborative process that honors each child’s uniqueness. By combining rigorous tools with empathetic observation, therapists create a roadmap that leads to meaningful outcomes. Whether you’re a clinician refining your protocol or a parent preparing for an evaluation, understanding this format helps set the stage for success. Always seek providers who prioritize transparency, cultural sensitivity, and ongoing communication throughout the assessment journey.