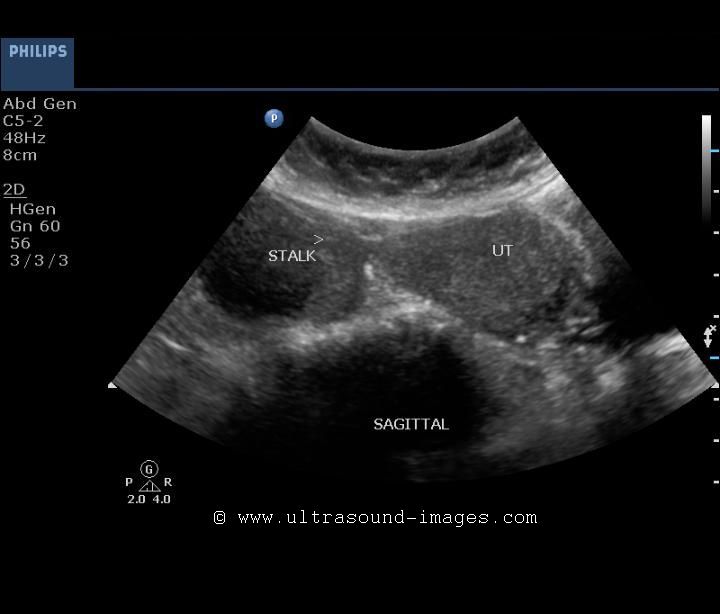
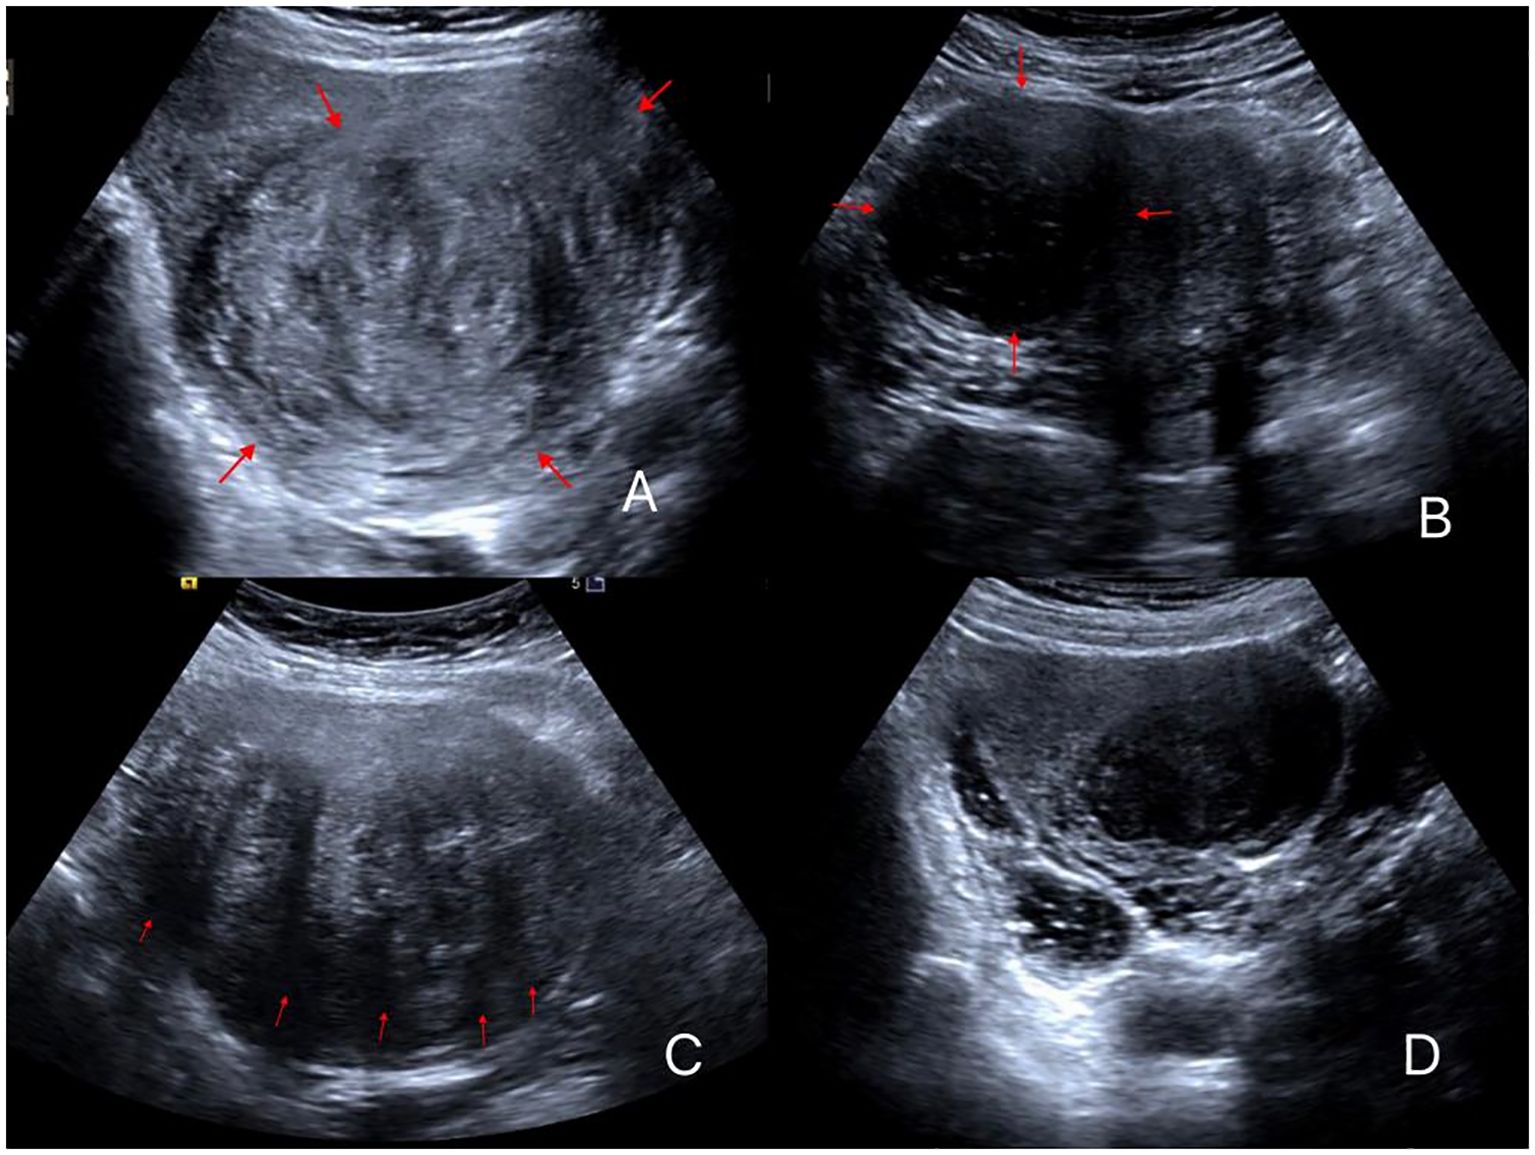
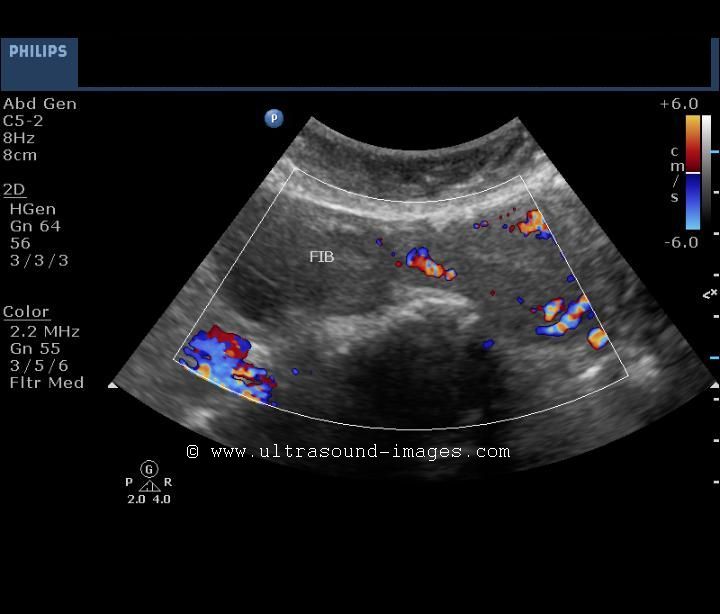
Uterine fibroids are among the most common benign tumors affecting women of reproductive age, and their accurate diagnosis heavily relies on imaging techniques—particularly ultrasound. Among the various types, pedunculated fibroids present unique challenges and distinctive sonographic features that radiologists and gynecologists must recognize promptly. A pedunculated fibroid is one that grows on a stalk (peduncle), either within the uterine cavity (submucosal) or extending into the abdominal cavity (subserosal). Understanding how these masses appear on ultrasound is essential for appropriate clinical management and surgical planning.
What Are Pedunculated Fibroids?
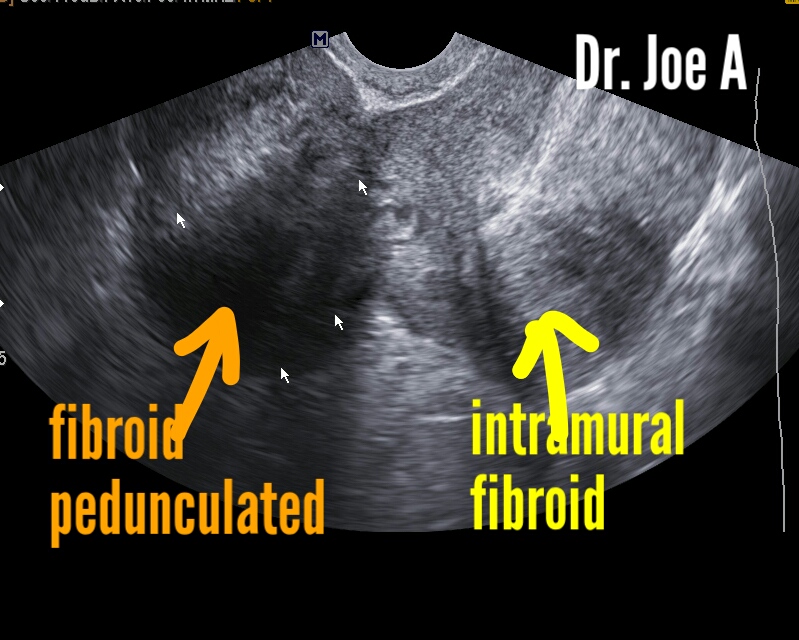
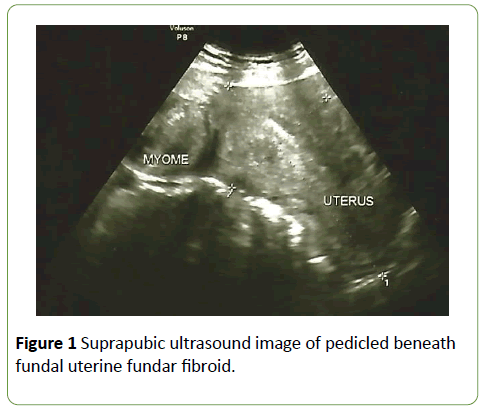
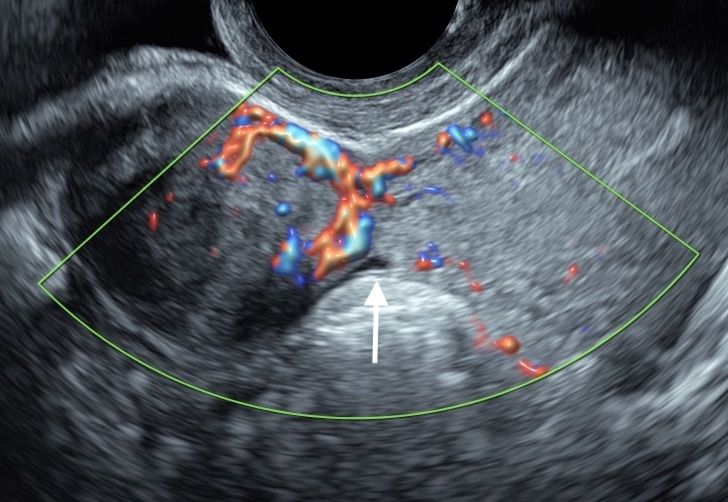
Pedunculated fibroids are a morphological variant of leiomyomas distinguished by their attachment via a narrow or broad-based stalk. When located outside the uterus, they can sometimes mimic ovarian tumors or other pelvic masses, making imaging interpretation critical. On ultrasound, they typically appear as well-defined, solid masses with heterogeneous echotexture. The key diagnostic clue lies in identifying the connection between the mass and the myometrium—this vascular pedicle can often be demonstrated using Doppler imaging, which helps differentiate pedunculated fibroids from other adnexal masses.
Key Ultrasound Features of Pedunculated Fibroids
Transvaginal ultrasound (TVUS) remains the first-line imaging modality for evaluating uterine fibroids due to its high resolution and proximity to the pelvic organs. In cases of pedunculated fibroids, sonographers should look for several characteristic findings:

- Well-circumscribed margins: Unlike diffuse adenomyosis, pedunculated fibroids maintain clear borders.
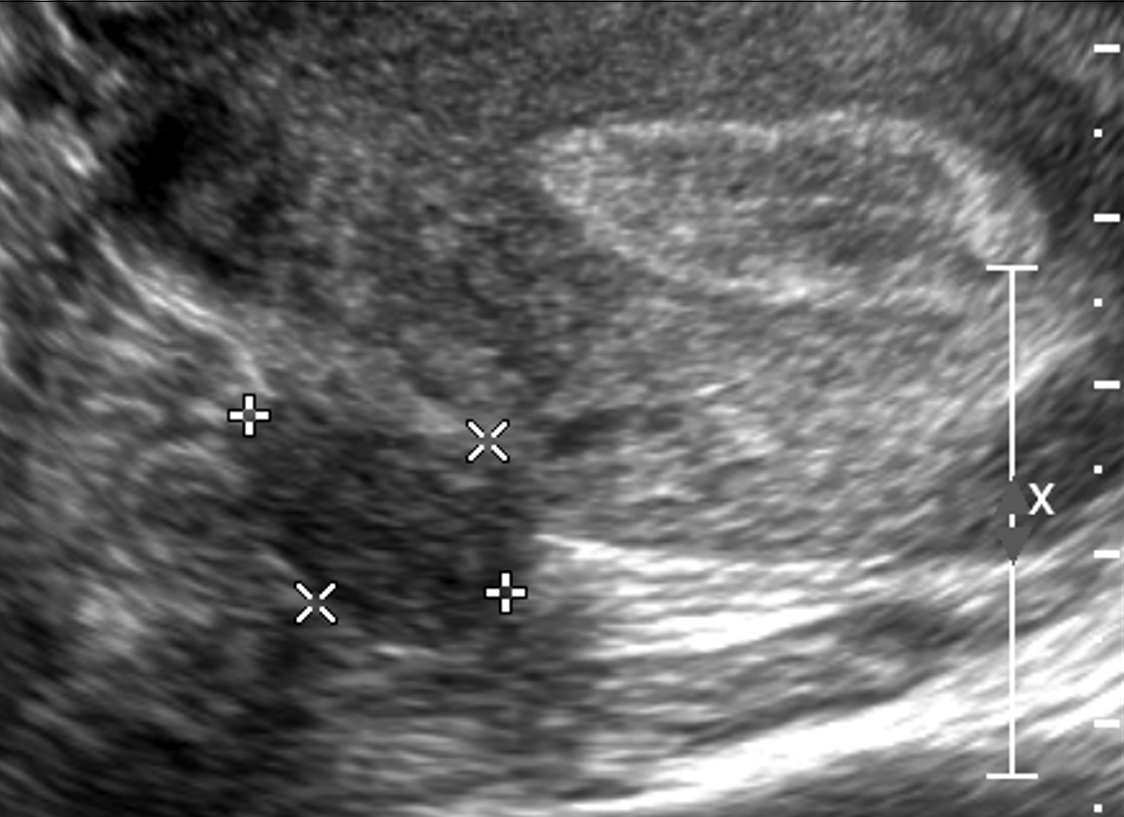
- Posterior acoustic shadowing: Calcified or dense fibroids may cast shadowing behind them.
- Heterogeneous internal echoes: Areas of degeneration (hyaline, cystic, or red degeneration) alter the usual echopattern.
- Visible pedicle: A thin or thick stalk connecting the mass to the uterine wall is pathognomonic when clearly visualized.
- Color Doppler signal: Peripheral or central vascularity within the pedicle confirms uterine origin.
Subserosal vs. Submucosal Pedunculated Fibroids on Imaging
Subserosal pedunculated fibroids project outward from the uterine surface and may become torsed, leading to acute pelvic pain. On ultrasound, torsion appears as reduced or absent blood flow in the pedicle. Submucosal pedunculated fibroids extend into the endometrial cavity and are frequently associated with heavy menstrual bleeding and infertility. These are best assessed using saline infusion sonohysterography (SIS), which enhances the visualization of the intracavitary component and the stalk’s attachment point within the endometrium.
Differential Diagnosis: Mimickers of Pedunculated Fibroids
Several pelvic masses can resemble pedunculated fibroids sonographically. Ovarian fibromas/thecomas, broad ligament fibroids, and even ectopic pregnancies (in rare torsion cases) must fall on the differential list. Table below summarizes distinguishing features:
| Feature | Pedunculated Fibroid | Ovarian Mass |
|---|---|---|
| Origin | Uterus (connected via pedicle) | Ovary |
| Doppler Flow | Peripheral/pedicle vessels | Central vascularity |
| Relation to Uterus | Mobile with uterus on probe pressure | Independent movement |
Clinical Implications of Accurate Ultrasound Diagnosis
Misdiagnosing a pedunculated fibroid can lead to unnecessary surgery for suspected malignancy or delayed intervention for torsion. Radiologists must document the size, location, vascularity, and relationship to surrounding structures. In equivotic cases, MRI serves as a complementary tool, offering superior soft-tissue contrast and the ability to confirm uterine origin even when the pedicle is not clearly seen on ultrasound. However, ultrasound remains the cornerstone due to its accessibility, real-time capabilities, and cost-effectiveness.

Emerging Techniques and Future Directions
Contrast-enhanced ultrasound (CEUS) and elastography are gaining traction in fibroid characterization. CEUS can delineate perfusion patterns in the pedicle and help distinguish viable fibroids from necrotic or degenerated ones. Elastography quantifies tissue stiffness, offering insights into fibroid composition without radiation exposure. As AI-assisted image analysis matures, automated detection of pedunculated morphology may improve diagnostic consistency across less-experienced operators.
Mastering the ultrasound appearance of pedunculated fibroids isn’t just academic—it directly impacts patient outcomes. Whether guiding a minimally invasive myomectomy or ruling out malignancy, precise imaging interpretation ensures timely, targeted care. For clinicians and sonographers alike, familiarity with the nuances of pedunculated fibroid ultrasound images is not optional; it’s foundational.