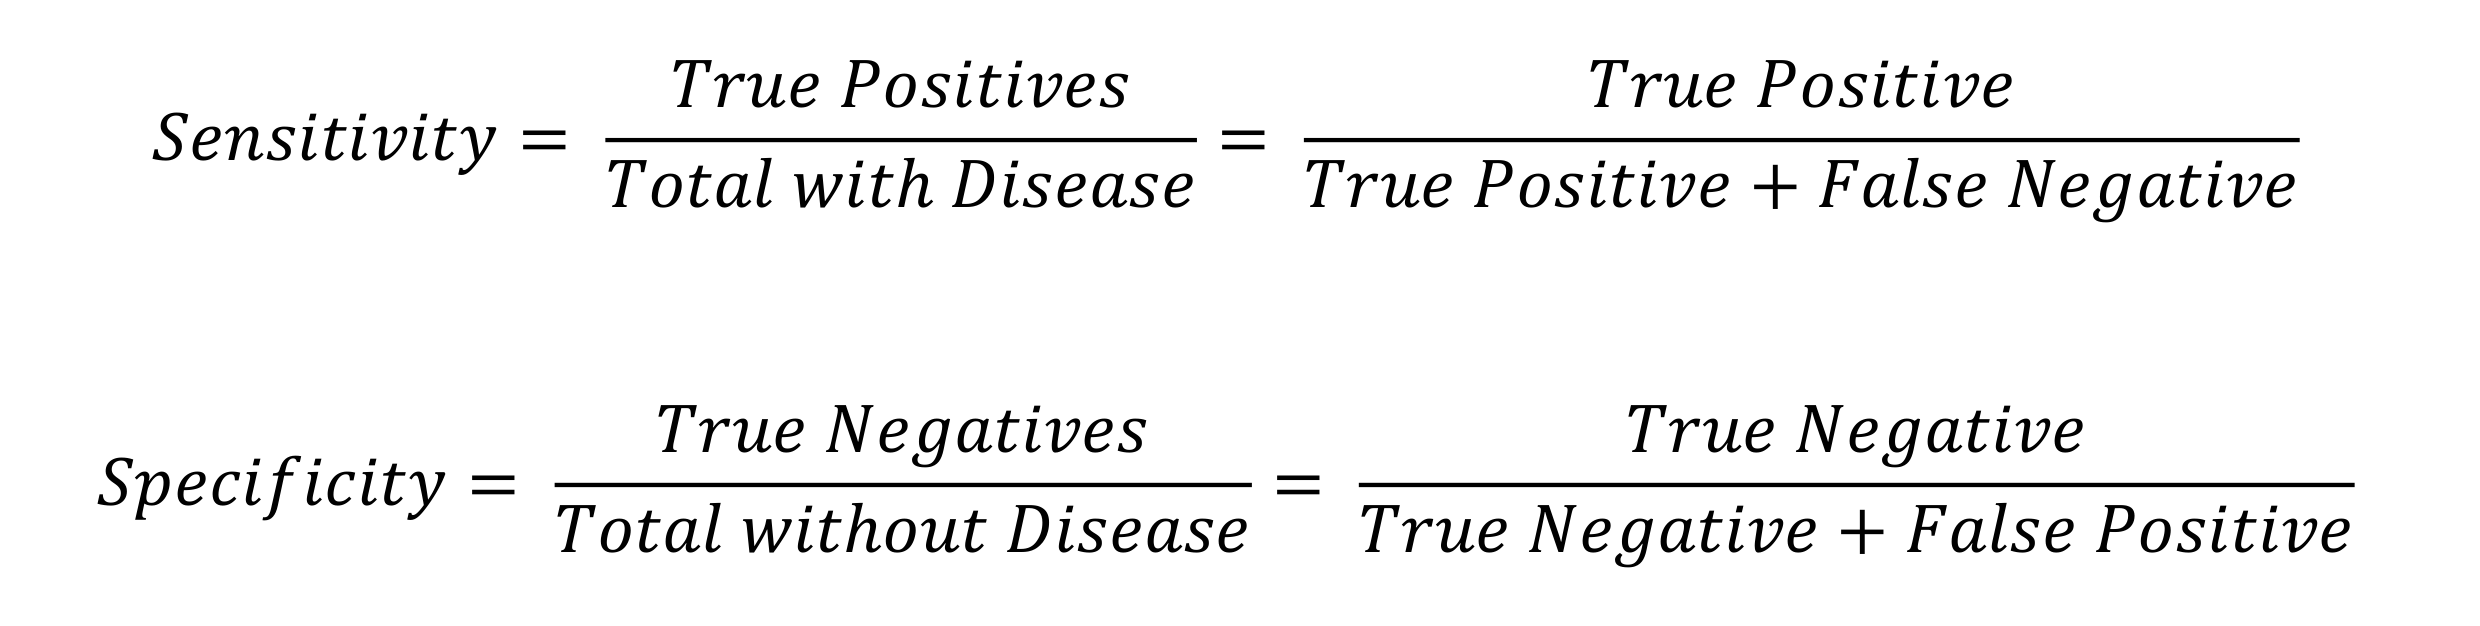Understanding Sensitivity and Specificity: A Comprehensive Guide
In the realm of diagnostic tests and predictive models, two key performance metrics stand out: sensitivity and specificity. These measures are crucial for evaluating the accuracy and reliability of a test or model. This article delves into the intricacies of sensitivity and specificity, their relationship, and how to interpret them using a sensitivity vs specificity table.
Defining Sensitivity and Specificity
Before we dive into the table, let's first understand these two terms:
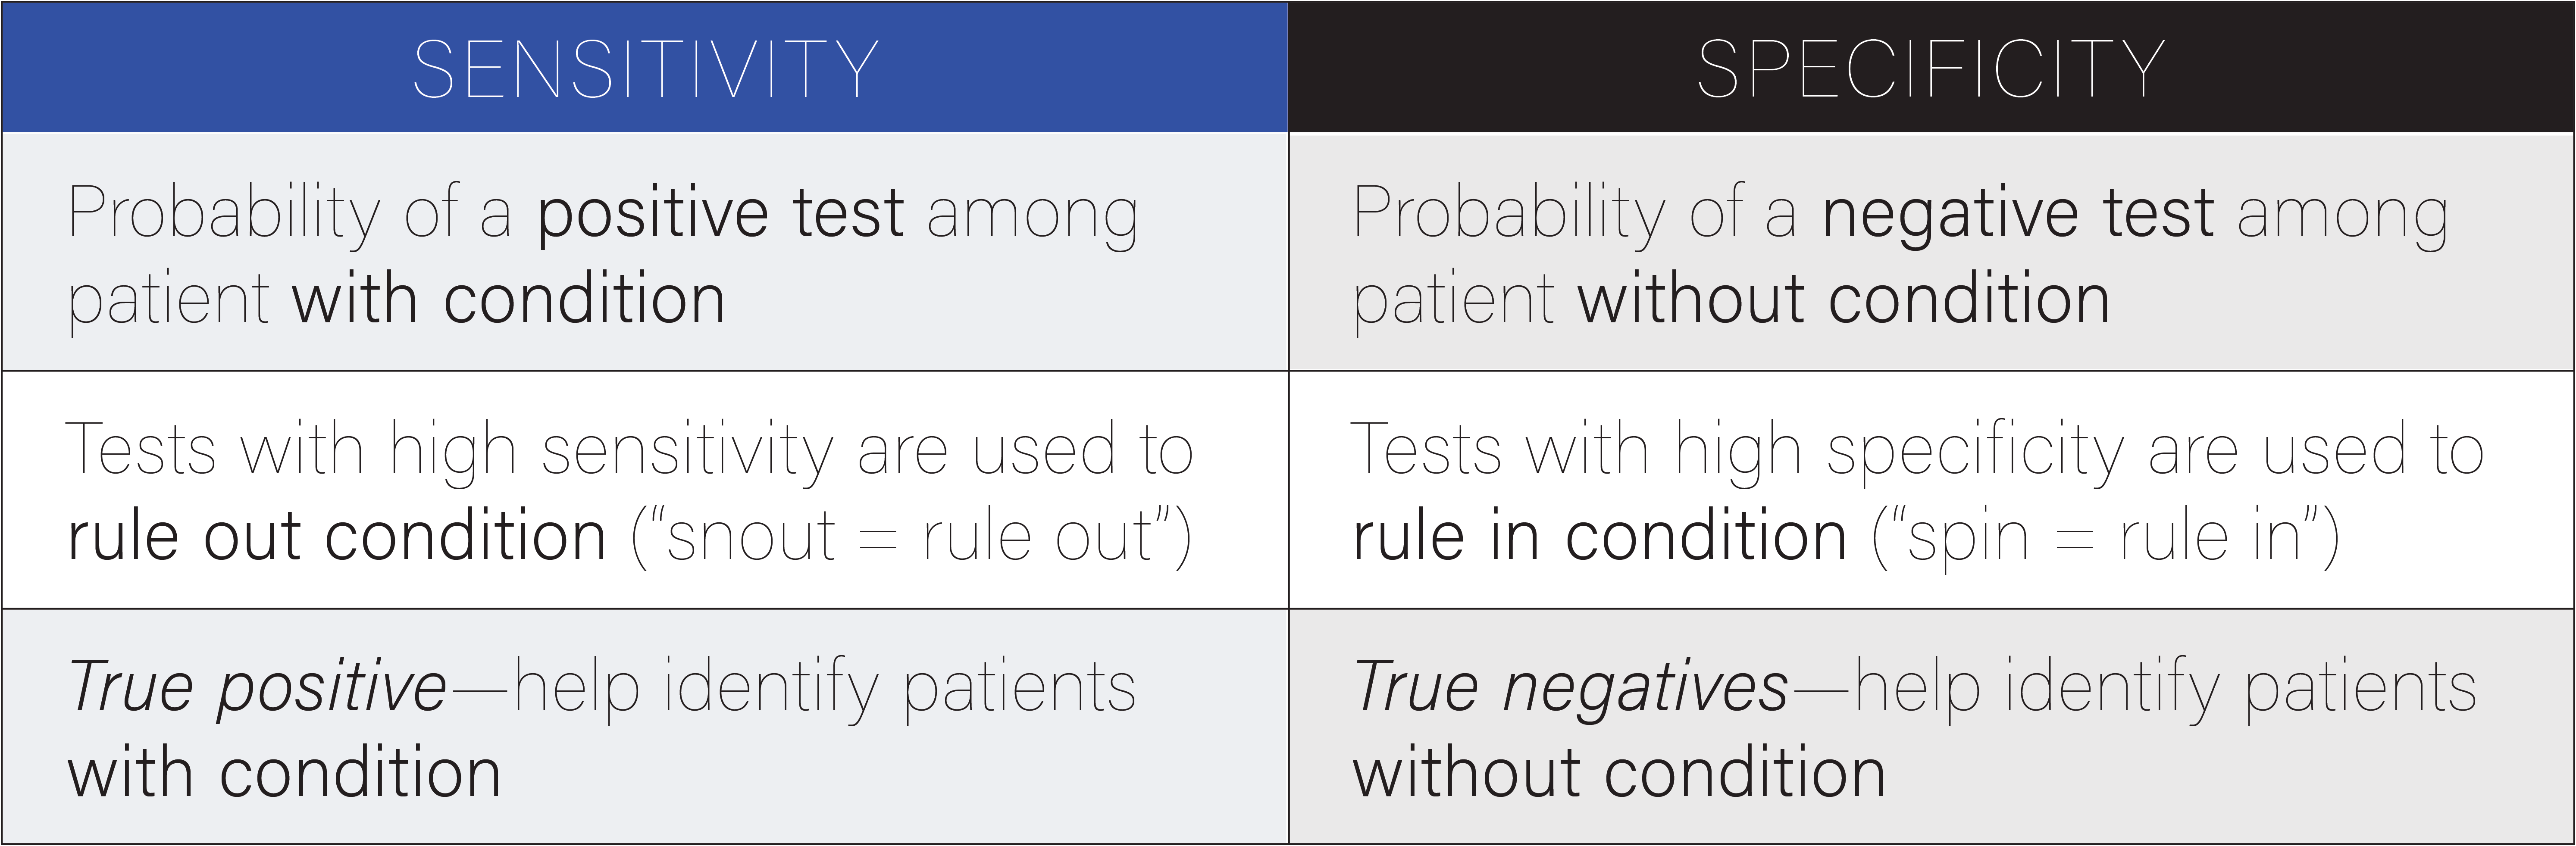
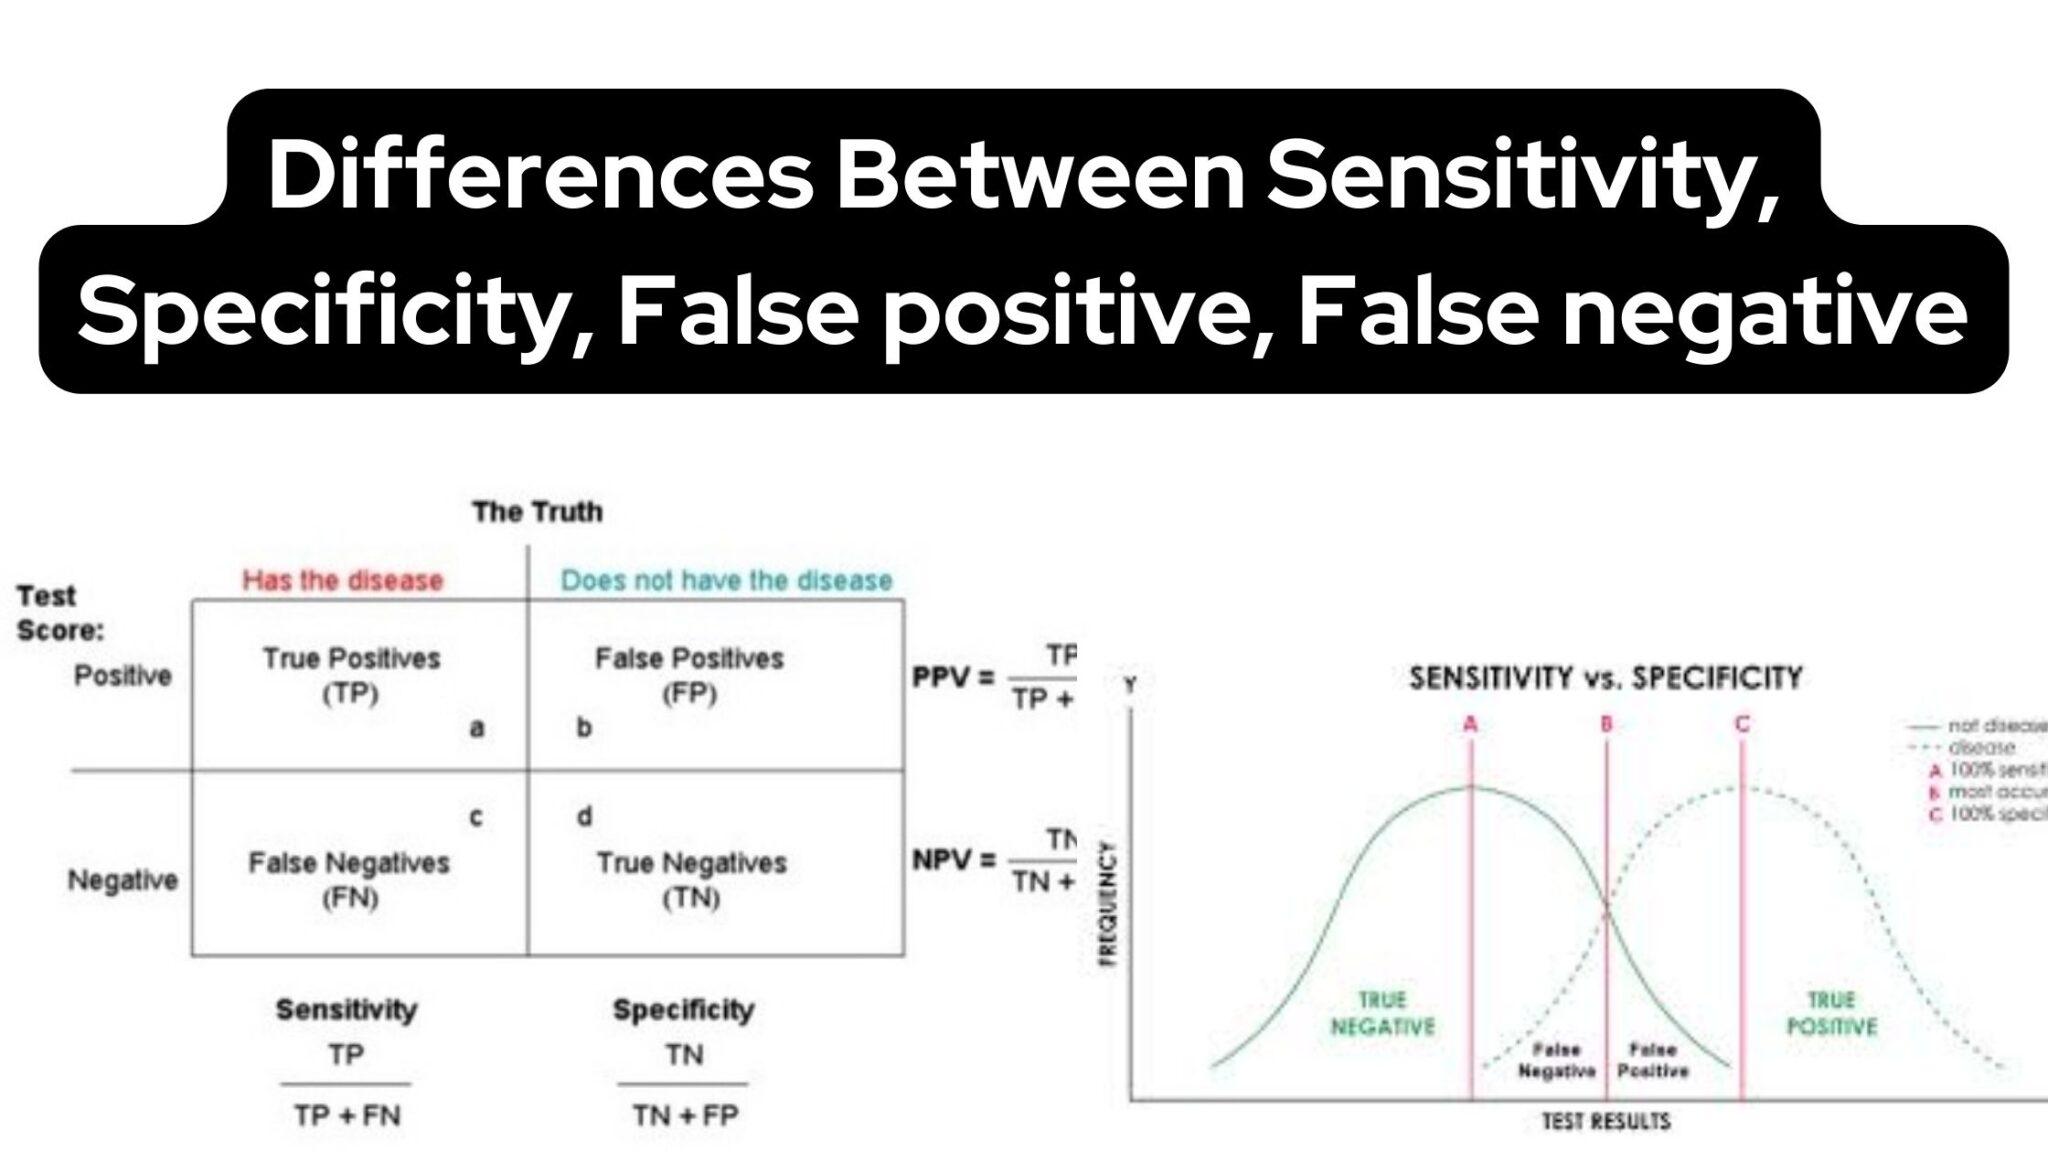
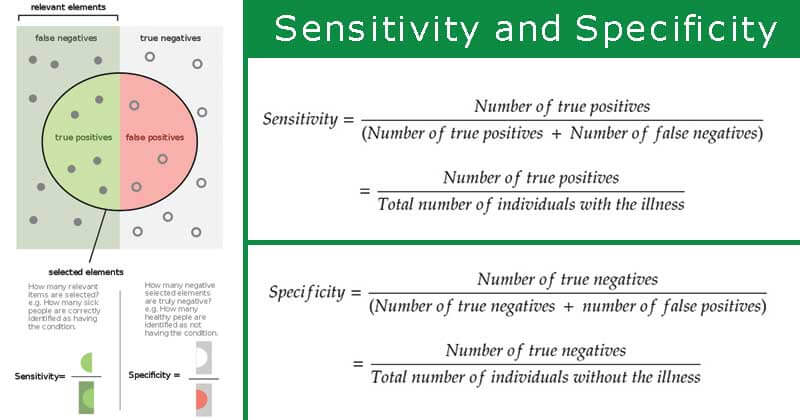
- Sensitivity: This measures the proportion of actual positives that are correctly identified as such (true positives) by the test or model. In other words, it's the ability of the test to identify all sick individuals.
- Specificity: This measures the proportion of actual negatives that are correctly identified as such (true negatives) by the test or model. It's the ability of the test to identify all healthy individuals.
Both sensitivity and specificity are expressed as percentages, with higher values indicating better performance.

Sensitivity vs Specificity: The Trade-off
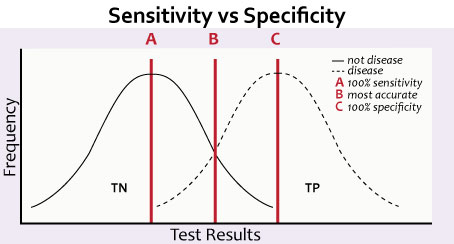
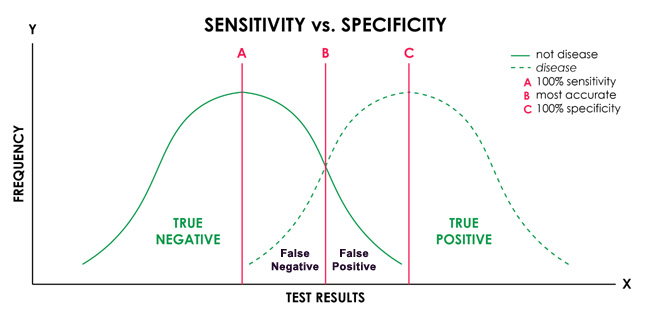
While it's ideal to have high values for both sensitivity and specificity, there's often a trade-off between the two. This is because increasing the sensitivity of a test can sometimes decrease its specificity, and vice versa. This trade-off is a key aspect to consider when interpreting a sensitivity vs specificity table.
Confusion Matrix: The Foundation of Sensitivity and Specificity
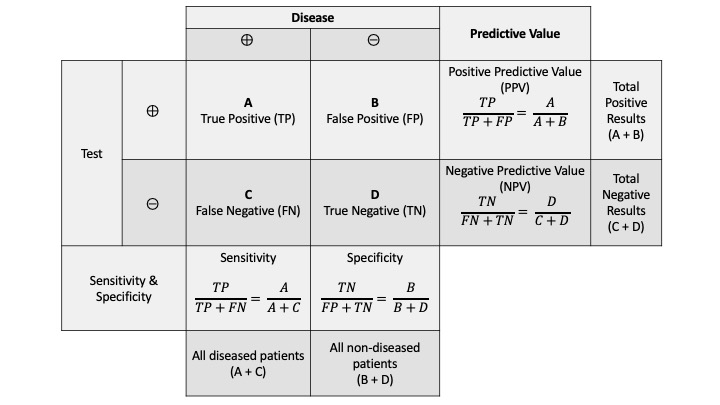
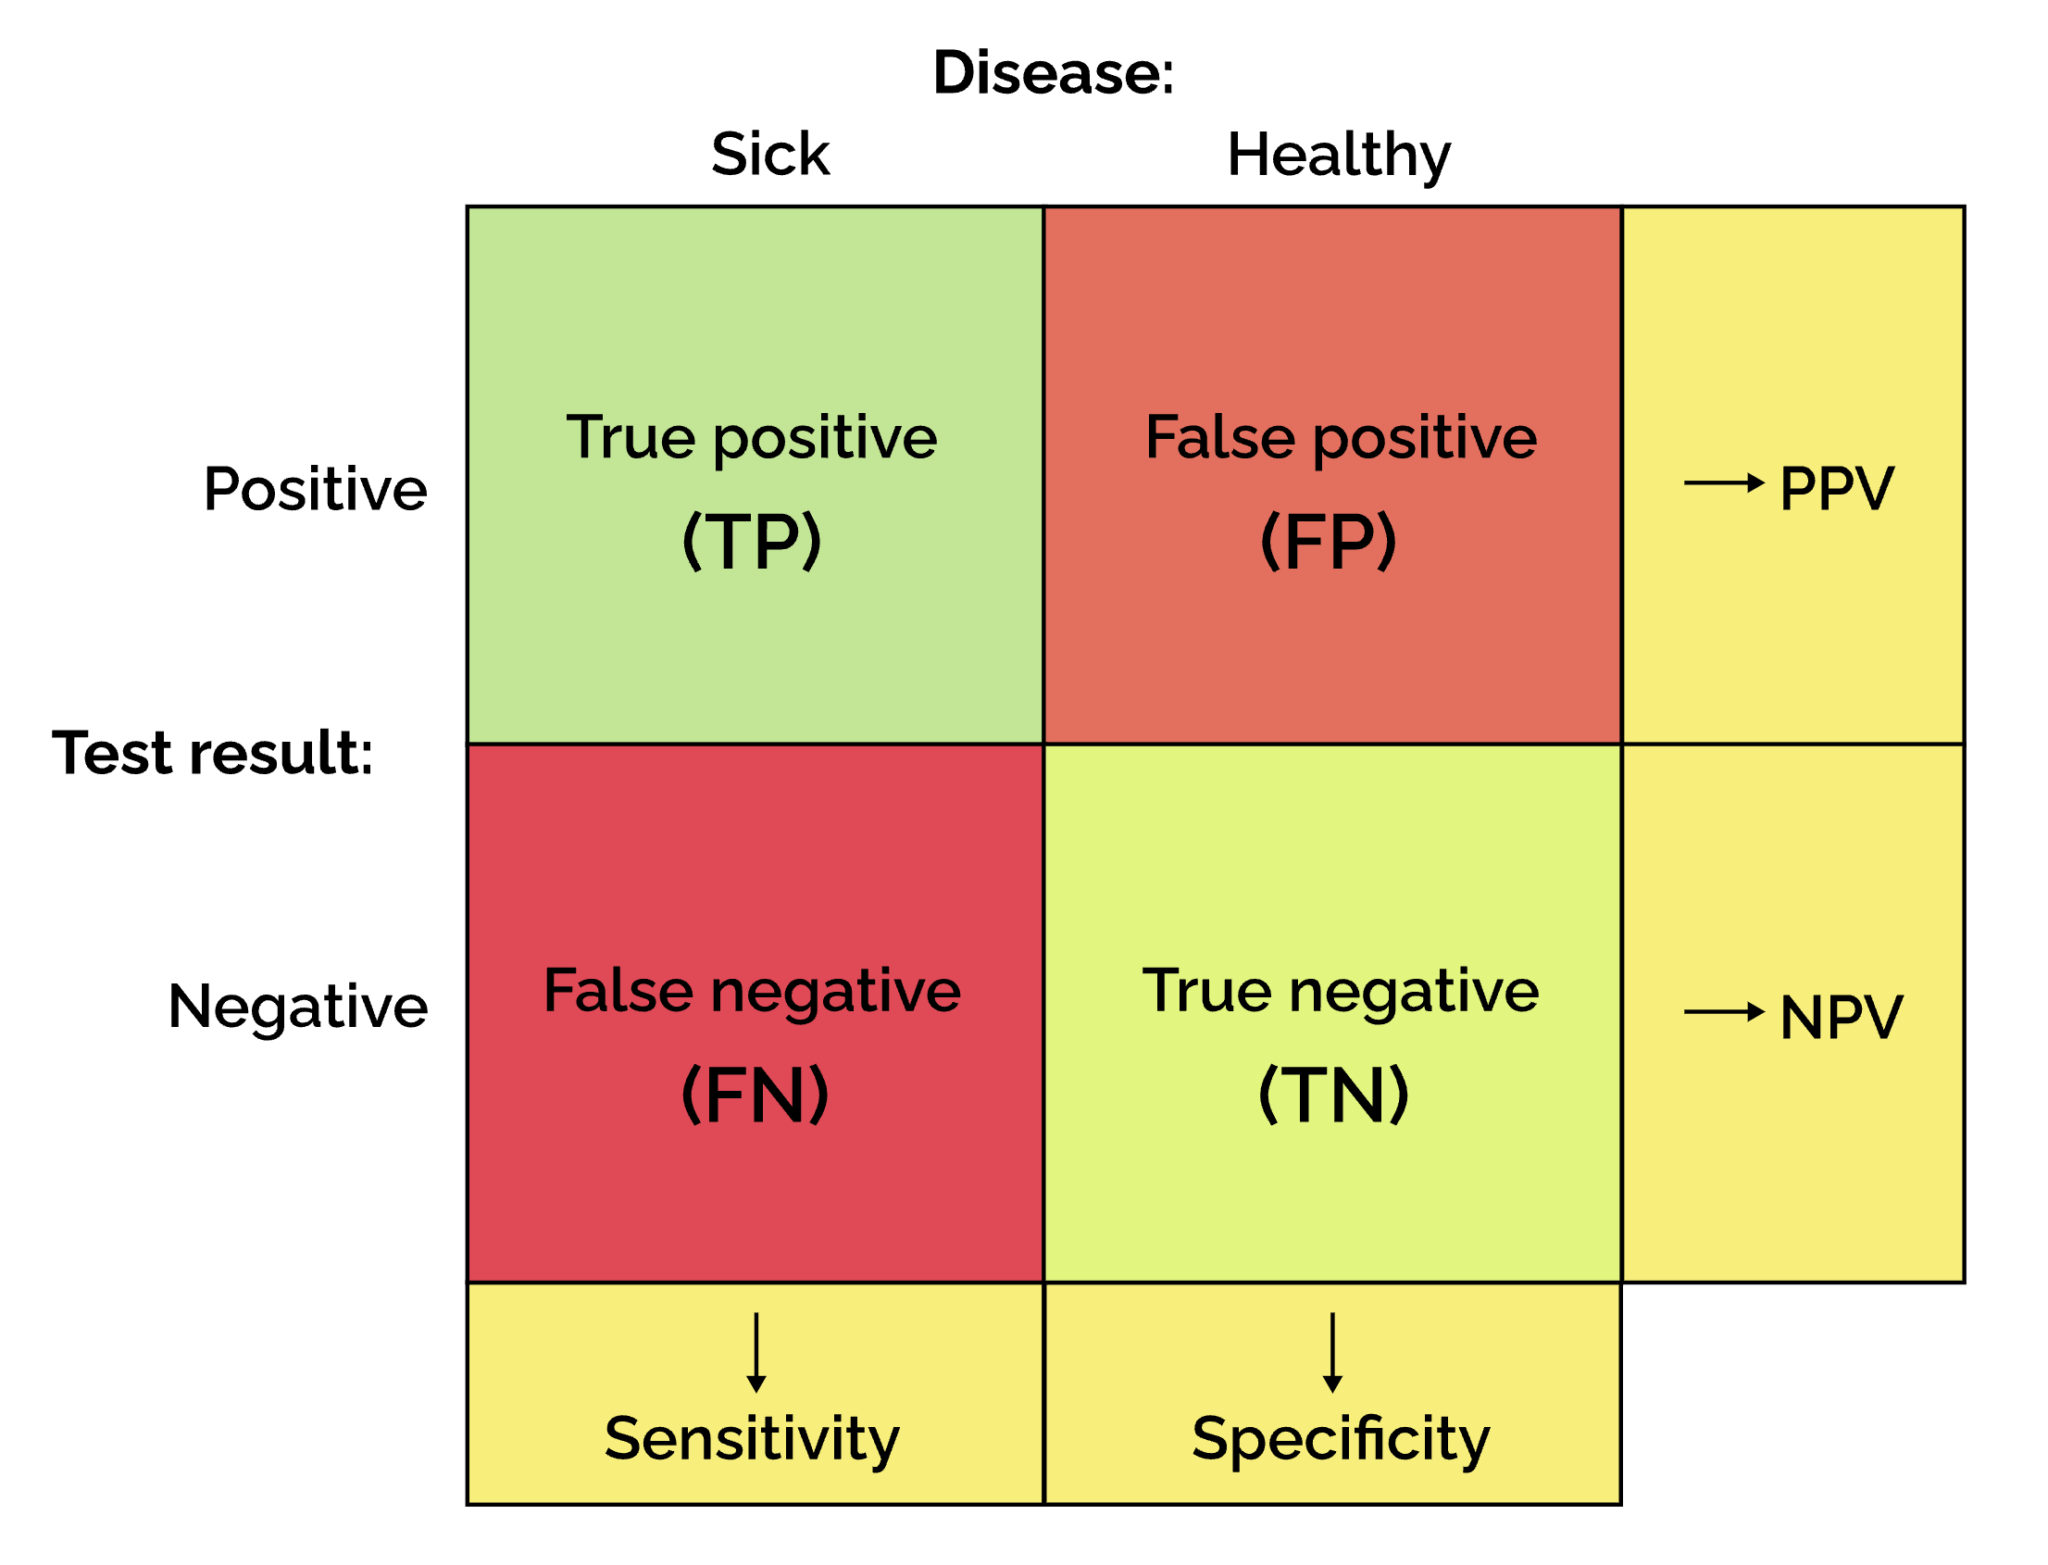
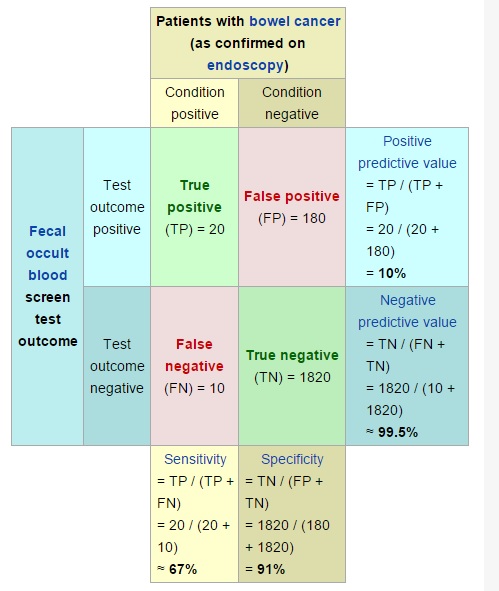
To understand the sensitivity vs specificity table, we first need to understand the confusion matrix, which is the foundation of these metrics. A confusion matrix is a table that describes the performance of a classification model (like a diagnostic test) on a set of test data for which the true values are known:
| Actual Positive | Actual Negative | |
|---|---|---|
| Predicted Positive | True Positive (TP) | False Positive (FP) |
| Predicted Negative | False Negative (FN) | True Negative (TN) |
Sensitivity and specificity are calculated using these values:

- Sensitivity = TP / (TP + FN)
- Specificity = TN / (TN + FP)
Interpreting the Sensitivity vs Specificity Table
A sensitivity vs specificity table typically presents these metrics for different cut-off points or thresholds of a test. Here's how to interpret such a table:
| Cut-off Point | Sensitivity (%) | Specificity (%) |
|---|---|---|
| 1 | 90 | 50 |
| 2 | 80 | 60 |
| 3 | 70 | 70 |
| 4 | 60 | 80 |
| 5 | 50 | 90 |
In this table, as the cut-off point increases, sensitivity decreases, but specificity increases. This illustrates the trade-off between sensitivity and specificity. The optimal cut-off point depends on the context and the relative importance of correctly identifying sick individuals (high sensitivity) vs. correctly identifying healthy individuals (high specificity).
Receiver Operating Characteristic (ROC) Curve: Visualizing Sensitivity vs Specificity
Another way to visualize the sensitivity vs specificity relationship is through a Receiver Operating Characteristic (ROC) curve. This is a plot of the true positive rate (TPR, which is equivalent to sensitivity) against the false positive rate (FPR) at various thresholds. The area under the ROC curve (AUC) provides a single measure of the test's accuracy, with higher AUC values indicating better performance.
In conclusion, understanding sensitivity and specificity, and how to interpret a sensitivity vs specificity table, is crucial for evaluating the performance of diagnostic tests and predictive models. By considering the trade-off between these two metrics, we can make more informed decisions about the optimal cut-off point for a test or model.