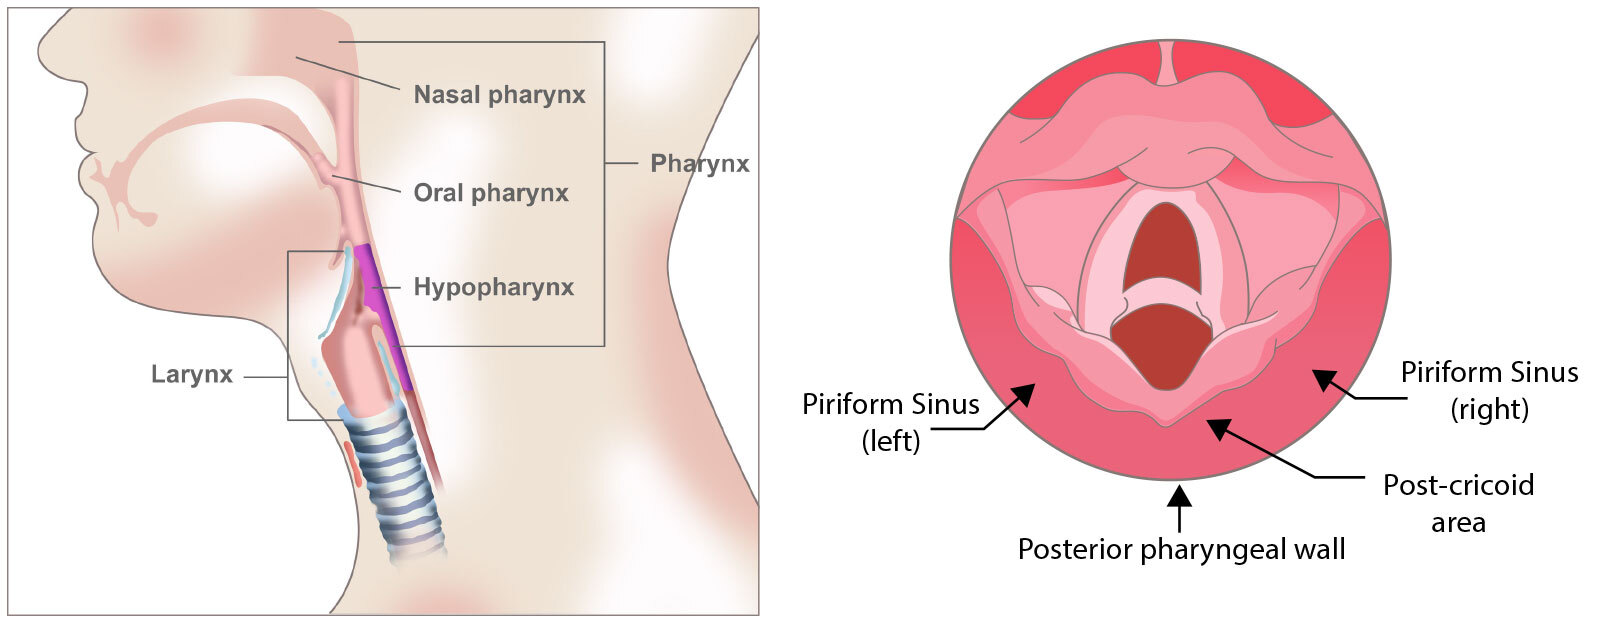
Lymphoid hyperplasia of the posterior pharyngeal wall is a common yet frequently overlooked condition affecting individuals across various age groups, with particular prevalence among adults in their third to fifth decades of life. This benign proliferation of lymphoid tissue, while often innocuous, can cause significant symptoms and diagnostic confusion. Understanding its clinical presentation, differential diagnosis, and management proves essential for healthcare providers and patients alike.
Understanding Lymphoid Hyperplasia in the Pharynx
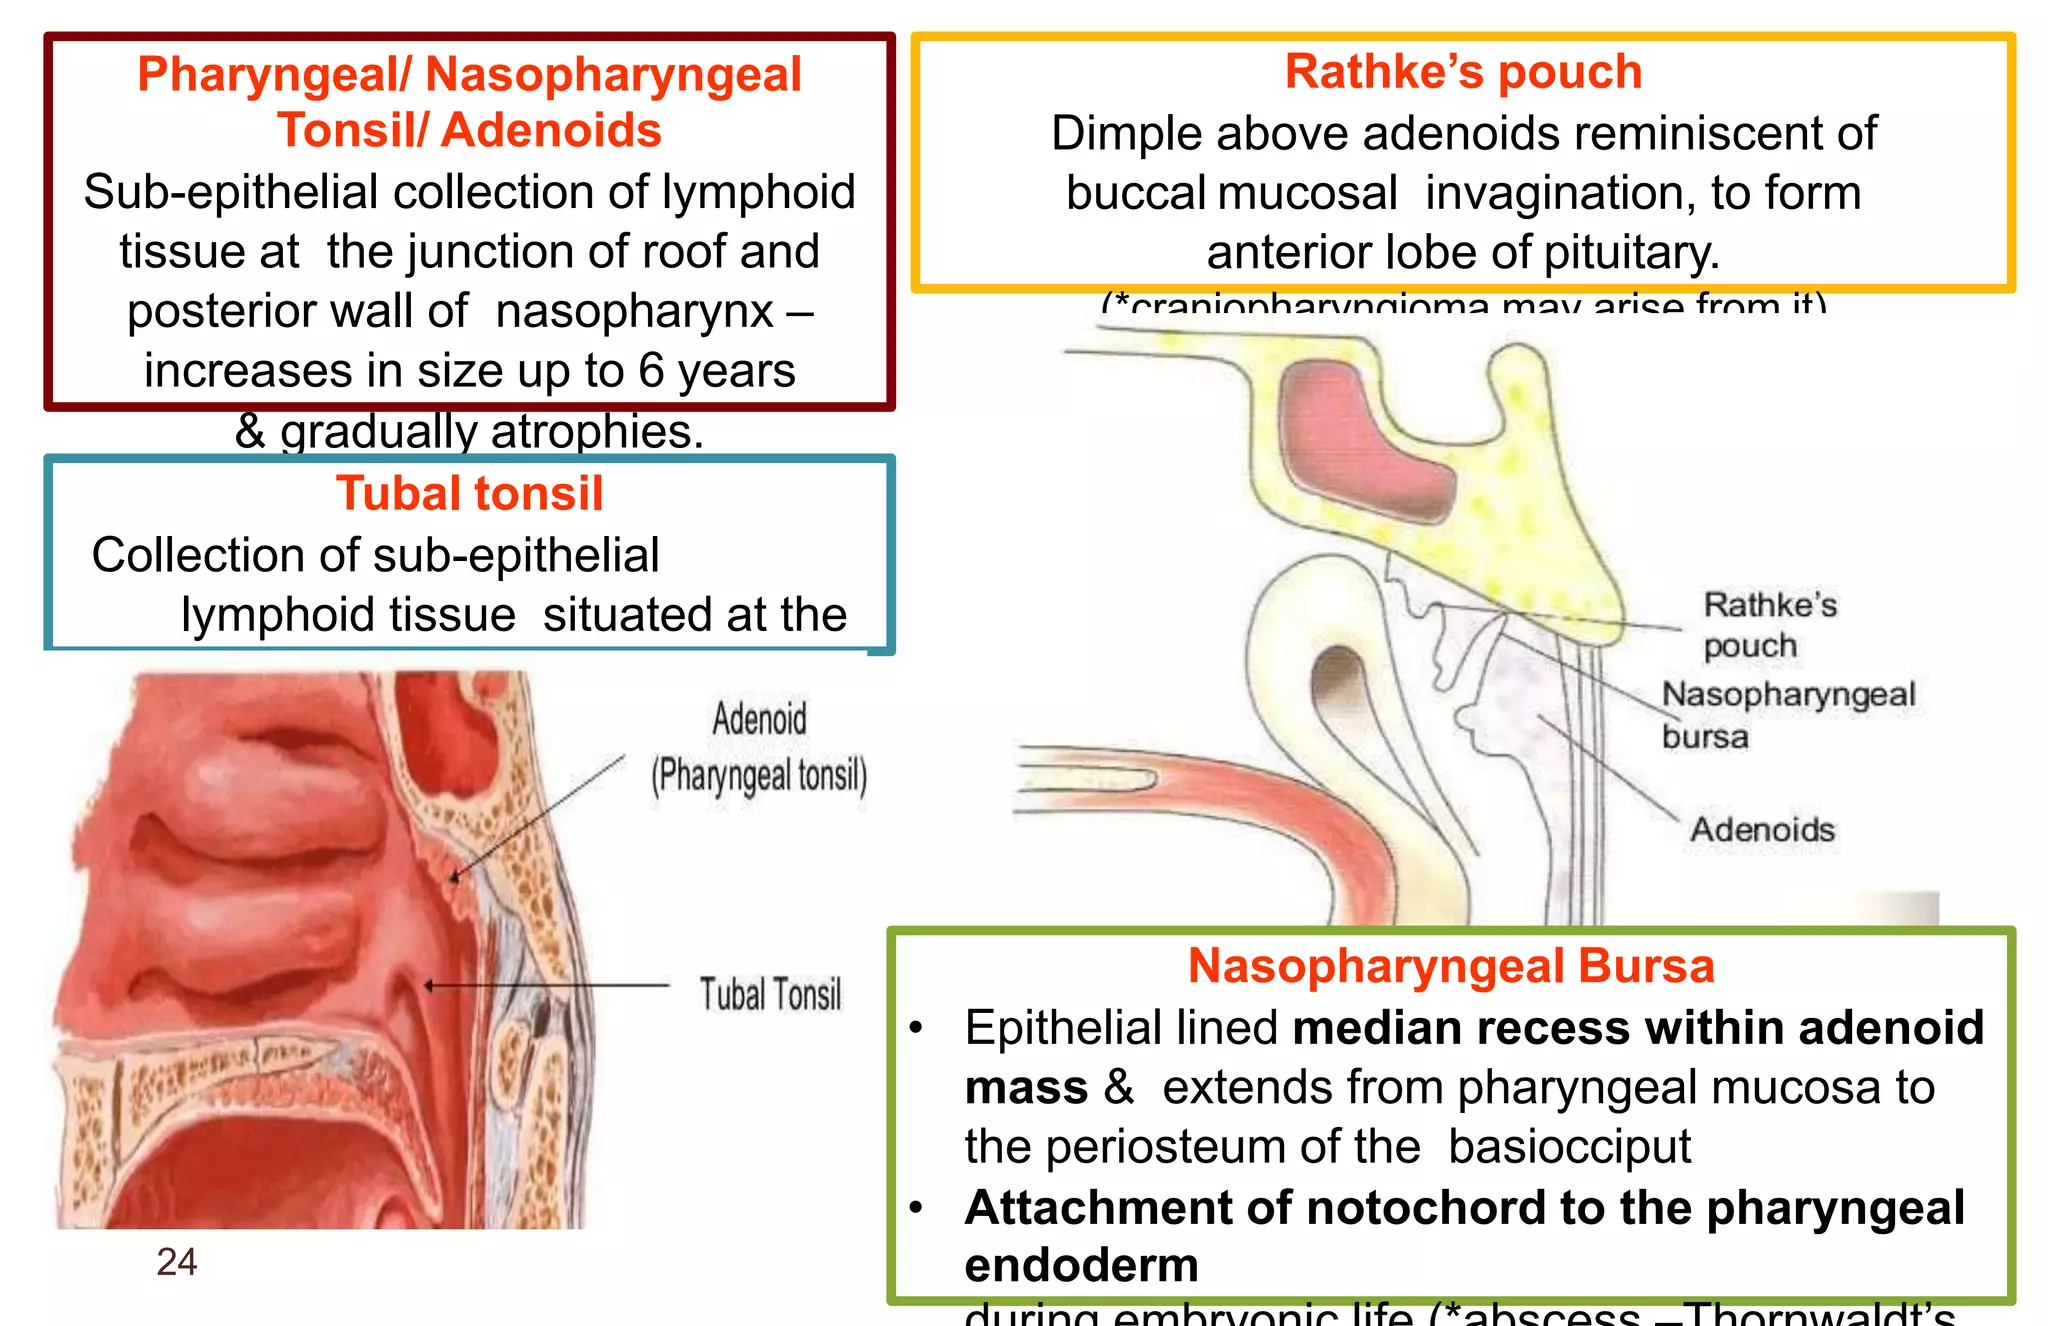
The posterior pharyngeal wall contains abundant lymphoid tissue that forms part of Waldeyer's ring, an anatomical structure serving crucial immune functions in the upper aerodigestive tract. Lymphoid hyperplasia represents an exaggerated immune response where these tissue collections enlarge beyond their normal dimensions. Unlike malignant lymphoid proliferation, this condition remains confined to reactive growth patterns without cellular atypia or clonal expansion.
Pathophysiology and Mechanisms
Several factors drive lymphoid hyperplasia development in the posterior pharyngeal wall. Chronic antigenic stimulation from infections, allergens, or environmental irritants triggers immune cell proliferation and tissue expansion. Gastroesophageal reflux disease (GERD) deserves particular attention, as laryngopharyngeal reflux exposes the posterior pharynx to gastric acid and pepsin, promoting chronic inflammation and subsequent lymphoid tissue growth. Additionally, immunoglobulin A (IgA) deficiency and other immunocompromised states increase susceptibility to recurrent infections that perpetuate this cycle.

Clinical Presentation and Symptoms
Patients with posterior pharyngeal wall lymphoid hyperplasia frequently report a constellation of upper aerodigestive complaints. Dysphagia, sensation of pharyngeal fullness, and chronic throat clearing dominate the symptom profile. Some individuals experience odynophagia (painful swallowing), particularly when hyperplasia becomes pronounced. Less common presentations include globus pharyngeus (lump sensation in the throat), voice changes, and nocturnal cough interfering with sleep quality.
The severity of symptoms correlates poorly with the degree of lymphoid tissue enlargement in many cases. Patients with modest hyperplasia may experience debilitating symptoms, while those with substantial tissue expansion remain asymptomatic. This dissociation complicates clinical decision making and underscores the importance of comprehensive evaluation.
Physical Examination Findings
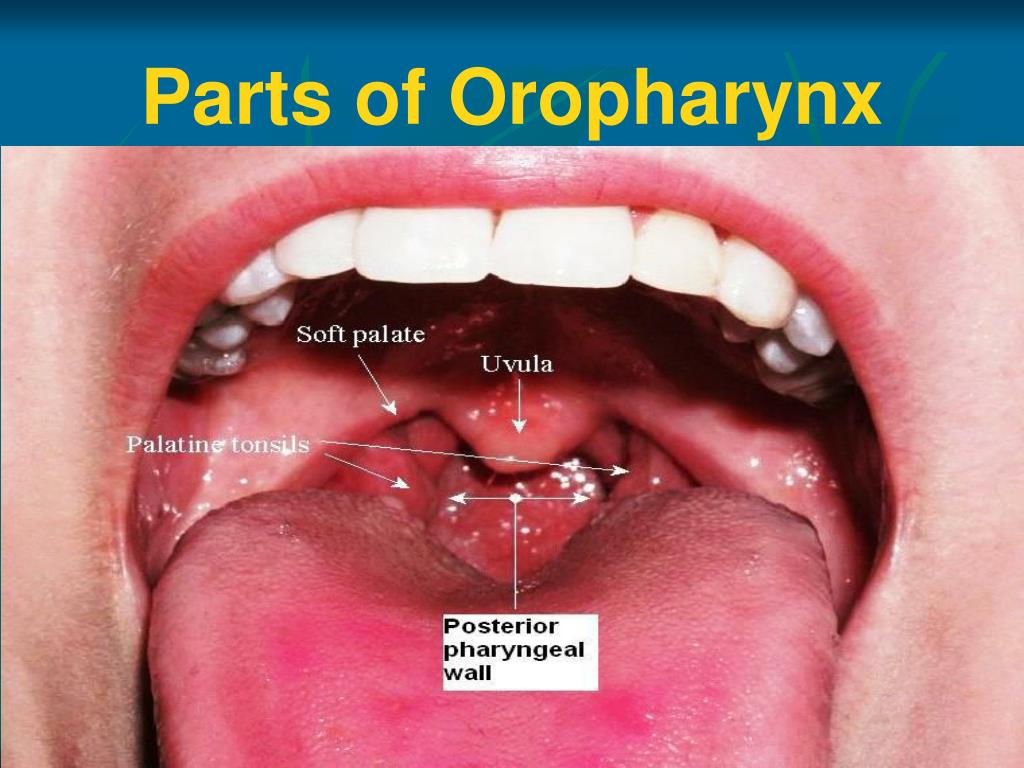
Oropharyngeal examination reveals characteristic cobblestone or nodular appearance of the posterior pharyngeal wall, reflecting the discrete lymphoid follicles undergoing compensatory hypertrophy. The surface mucosa remains intact, distinguishing this condition from ulcerative or neoplastic processes. Palpation demonstrates firm, non-tender consistency without fixation to underlying structures. Flexible nasopharyngolaryngoscopy extends visualization to assess the extent of lymphoid tissue involvement in the nasopharynx and hypopharynx.

Diagnostic Evaluation
Diagnosis relies primarily upon clinical examination, though ancillary testing helps exclude concurrent conditions and complications. Direct laryngoscopy permits detailed assessment and biopsy when tissue diagnosis becomes necessary. Fine-needle aspiration or excisional biopsy specimens demonstrate polyclonal lymphoid proliferation, follicular hyperplasia, and preserved tissue architecture without cytological atypia.
Radiological imaging proves generally unnecessary for isolated lymphoid hyperplasia but helps evaluate concurrent adenoidal hypertrophy or nasopharyngeal pathology. Computed tomography and magnetic resonance imaging delineate the extent of soft tissue involvement and exclude skull base erosion or deep space infection when clinical presentation raises such concerns.
Differential Diagnosis Considerations
| Condition | Distinguishing Features |
|---|---|
| Oropharyngeal squamous cell carcinoma | Ulceration, fixation, constitutional symptoms |
| Lymphoma | Extralymphatic involvement, Reed-Sternberg cells |
| Candidiasis | White pseudomembranes removable |
| Nasopharyngeal carcinoma | Eustachian tube dysfunction, cranial nerve palsy |
Distinguishing lymphoid hyperplasia from malignancy represents the paramount diagnostic challenge. Positron emission tomography combined with CT exhibits high sensitivity for malignant transformation, while elevated lactate dehydrogenase levels and monoclonal patterns on flow cytometry strongly suggest lymphomatous progression rather than benign reactive change.
Risk Factors for Malignant Transformation
While lymphoid hyperplasia itself conveys no malignant potential, certain clinical scenarios warrant heightened vigilance. Immunocompromised states, particularly HIV infection and post-transplant immunosuppression, substantially increase lymphoma risk. Extranodal NK/T-cell lymphoma, nasal type occurs preferentially in nasopharyngeal and oropharyngeal sites, demanding differentiation from benign proliferation. Chronic Epstein-Barr virus infection warrants monitoring through tissue viral loads and IgA antibody titers.
Management Strategies
Treatment approaches vary dramatically based upon symptom severity and underlying etiology. Asymptomatic patients require observation alone, with periodic reassessment to document stability. When conservative measures fail, directed therapy for modifiable causative factors predominates.
- PPI therapy and smoking cessation for laryngopharyngeal reflux
- Allergen immunotherapy for IgE-mediated allergic rhinitis triggering pharyngeal immune stimulation
- Topical corticosteroids reduce associated mucosal edema and inflammatory cytokine production
- Watchful waiting with serial examinations every 6-12 months
Surgical Intervention
Refractory cases causing airway compromise, obstructive sleep apnea, or debilitating dysphagia may require surgical intervention. CO2 laser ablation permits precise tissue removal with excellent hemostasis and minimal collateral thermal damage. Coblation technology offers comparable outcomes with potentially reduced postoperative pain. Radiofrequency ablation provides effective tissue reduction without general anesthesia requirements, suitable for office-based procedures.
Prognosis and Surveillance
The prognosis for isolated lymphoid hyperplasia of the posterior pharyngeal wall remains excellent, with no increased malignancy risk demonstrated in immunocompetent populations. Patients should monitor for warning signs including rapid enlargement, unexplained weight loss, persistent fever, night sweats, or new cranial neuropathies. These findings necessitate urgent reevaluation with appropriate biopsy and imaging studies.
Regular follow-up examinations at intervals determined by initial clinical severity and risk factor burden ensure timely detection of improbable but consequential complications. Patient education regarding the benign nature of this condition reduces anxiety that frequently accompanies pharyngeal symptom evaluation and avoids unnecessary procedures driven by health anxiety.
Emerging Research Directions
Ongoing investigations explore lymphoid hyperplasia through molecular profiling techniques identifying personalized therapeutic targets and biomarkers predicting response to intervention. Preliminary data suggest promising outcomes with targeted biologic therapies in aggressive or recurrent cases, representing potential paradigm shifts for recalcitrant disease. Machine learning applications in pharyngeal imaging analysis may eventually automate detection and streamline diagnostic workflows.




_anatomical_landmarks_for_hogan_s_modification_to_the_superiorly_based_pharyngeal_flap__(.jpeg)